If you're like most of our patients, you got the MRI, got the diagnosis, and
then got a shrug: pills, a sheet of exercises, maybe a shot — and "come back if it gets
worse." There is a step between that and surgery. We've used it on more than 2,000 patients
since 2005. So has Dr. Barton — on his own herniated disc, one of the worst he had seen in
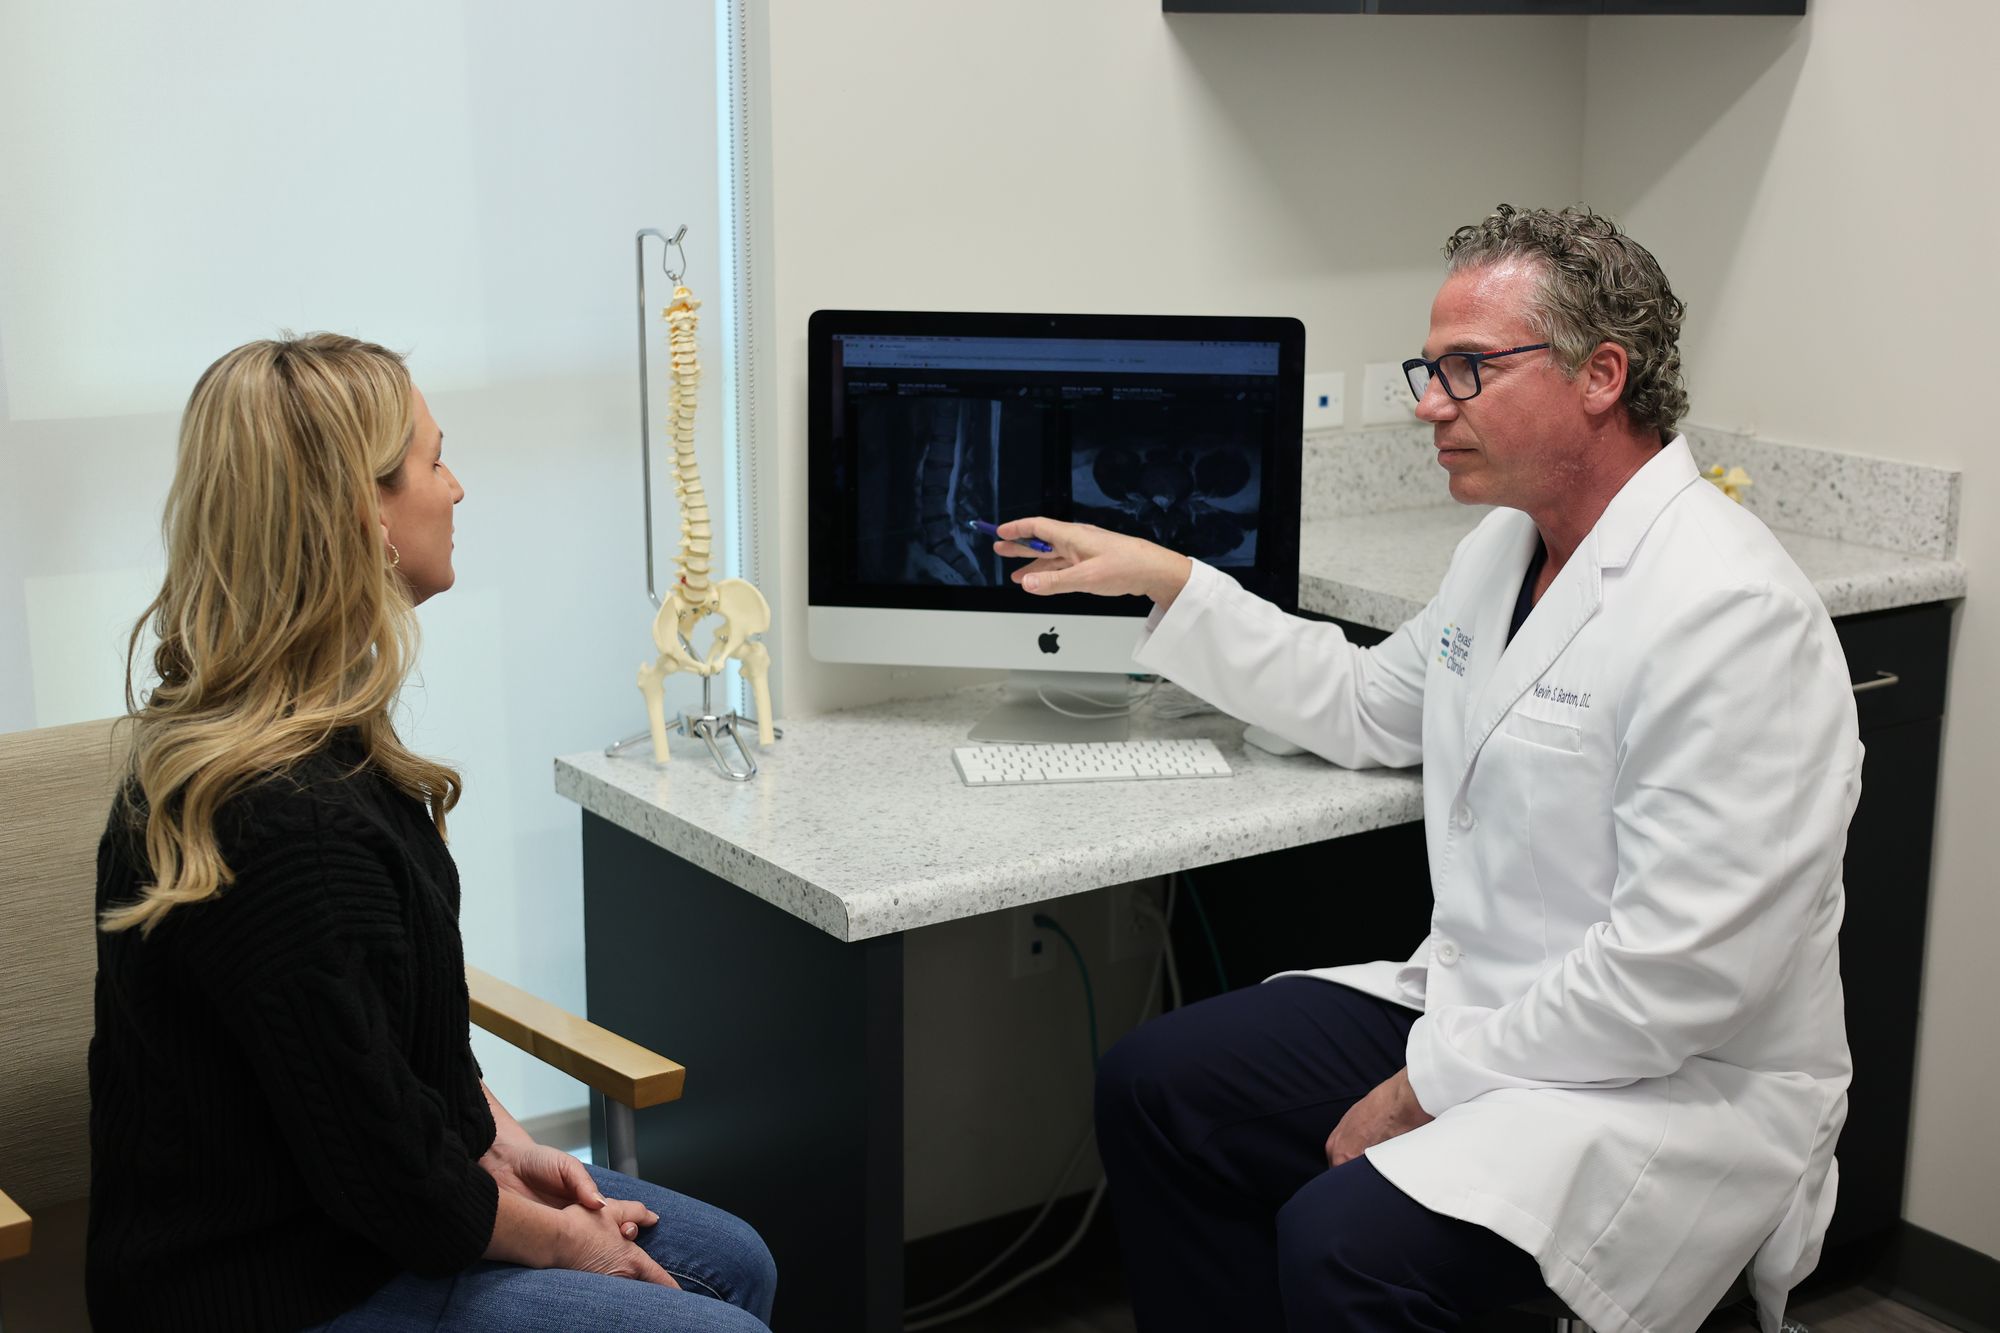
over 20 years of practice. Bring us your MRI. We'll put the pictures on the
screen — not just the report — and go through them out loud, with you in the
room.
23years in practice
21years using the DRX9000
2,000+patients treated on it
You probably remember the exact moment. Nothing heroic. You bent over to pick something up.
You stood up out of the car. You put your shoes on. And your back went out like a switch
flipped.
Since then your life has gotten smaller in ways nobody else can see. You put your socks on
lying down. You don't sit on the couch through a movie anymore — you end up on the floor.
You've stopped picking things up off the ground the normal way. And there's the 4am wake-up,
when the nerve starts talking and the rest of the night is gone.
Then came the wait for the MRI. And then something strange happened: the report was almost a
relief. Finally, proof. Something on a screen that says you weren't exaggerating.
And then you read it: herniation… protrusion… posterolateral… impinging the nerve root…
degenerative changes. Maybe someone spent ninety seconds on it. Maybe nobody went over
it at all — you requested the disc yourself and tried to decode it in the parking lot on
your phone.
So now you're carrying two fears at once. The fear of what the report says. And the fear
that the only real fix is surgery.
Neither fear is quite right. Let's take them in order —
starting with the report, because you shouldn't have to be afraid of a document nobody
explained to you.
Your MRI report, decoded
What your MRI report actually says, in plain English
Radiology reports are written by one doctor for
another, in a shorthand built to be precise, not comforting. Almost every frightening word
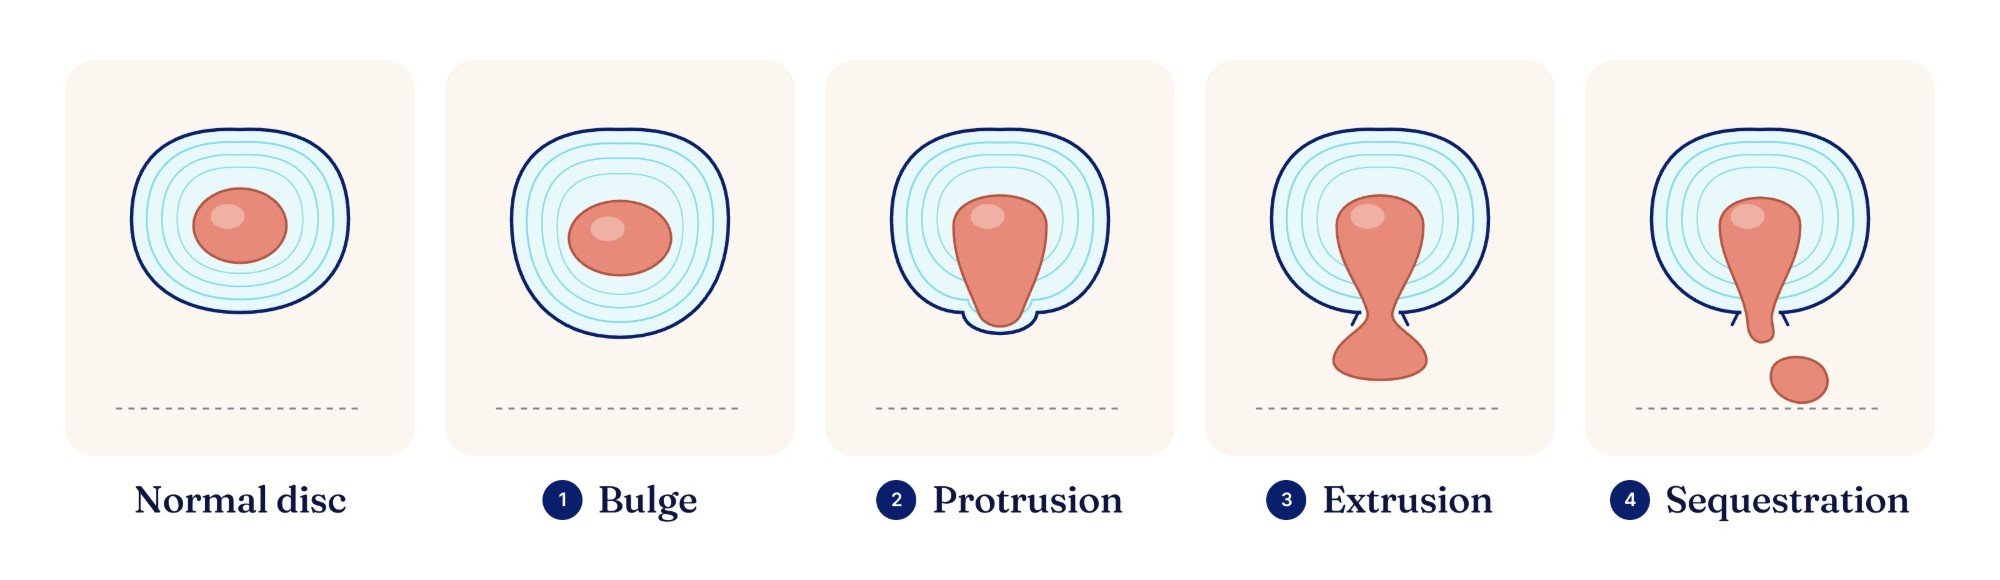
in yours has a boring meaning. The four you'll see most describe one ladder:
Size is the headline. Location is the story.
A 3mm herniation aimed into a tight nerve tunnel can hurt more than a 9mm one
pointed into open space.
"Degenerative" describes mileage, not a prophecy.
Disc bulges show up on 30% of pain-free 20-year-olds' MRIs, and 84% by age
80.6
The scan matters, and so does the exam.
These findings are more common in people who hurt,7
but a report alone never proves what's causing your pain.
One thing that does change the
plan: a fragment that has broken free (a sequestration) can be a reason we won't treat,
depending on your symptoms and its size. That's why we read your actual imaging before
anyone talks about treatment.
The body can break down and reabsorb herniated disc material. Your immune system treats
material that has escaped the disc as debris to be cleaned up, and over months it can shrink,
retract, and in some cases disappear from a follow-up scan. This is real, it is documented,
and any straight spine clinic will tell you so before taking your money.
Here's the strange part, and it's the same point from the ladder above: the more
dramatic the herniation, the better its odds of shrinking on its own. A large
extrusion or a free fragment is more exposed to your bloodstream, so there's more for the
body to go after. A contained protrusion, still sealed inside its shell, is the one more
likely to sit there.
So why not just wait?
Because of the part nobody can do for you: nobody can tell you in advance which
group you're in. Not us. Not your surgeon. Not the radiologist. There is no test
that sorts "this one will resolve by spring" from "this one will still be here in two
years." Both people walk into the office with the same report and the same story.
That leaves you choosing between two real risks, and you should choose with your eyes
open:
Wait, and you might get better for free. You might also spend another
year of your life on the floor next to the couch, and arrive at the same decision point in
twelve months with less muscle, more guarding, and a disc that has lost more height.
Treat it, and you'll never know for certain what would have happened
anyway.
What we can do is take the pressure off while your body does whatever it was going to do —
and give it better conditions to do it in. And we can tell you early whether your spine is
responding, instead of asking you to keep paying and hoping.
The real checkpoint: we assess whether your spine is
responding around the second week, after eight to ten sessions. If it isn't, we say so then —
not after another month of visits — and you don't pay for the rest.
Why it hasn't healed on its own: an injury that
stays under load
Here's the frustrating math of a herniated disc: it's an injury that never gets left
alone.
A cut on your arm heals because nothing keeps re-opening it. Your disc doesn't get that
chance. Every hour in a chair, every lift, every step keeps pressure on the exact spot that's
trying to heal. Then the muscles around it lock down to guard it, which loads everything even
harder. Then the small joints behind it stiffen up as the disc loses height. Four tissues —
disc, joint, nerve, muscle — all pulling each other down.
The four tissues, in full, on the DRX9000 page.
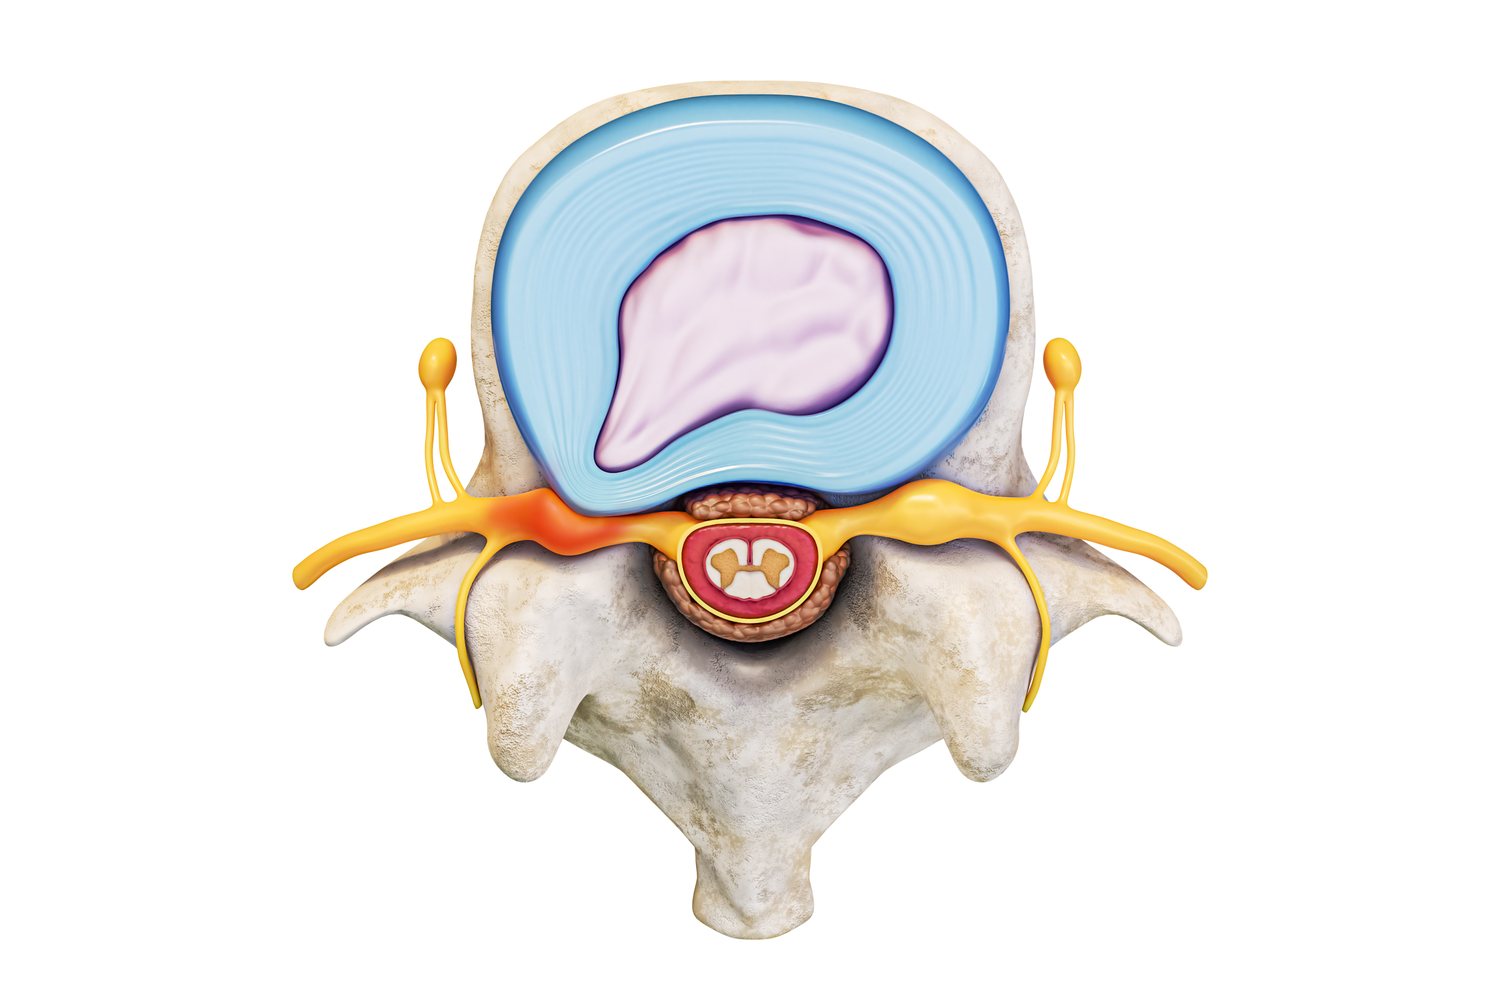
This is what your MRI report is describing. The disc's soft centre has pushed back through the outer wall, and where it reaches the nerve root, the root inflames. A herniation that isn't touching a nerve often causes nothing at all — it's contact that turns a finding into a problem.
If you had a bruise on your arm and somebody pressed a thumb into it
all day, every day, it would never heal either. That's your disc.
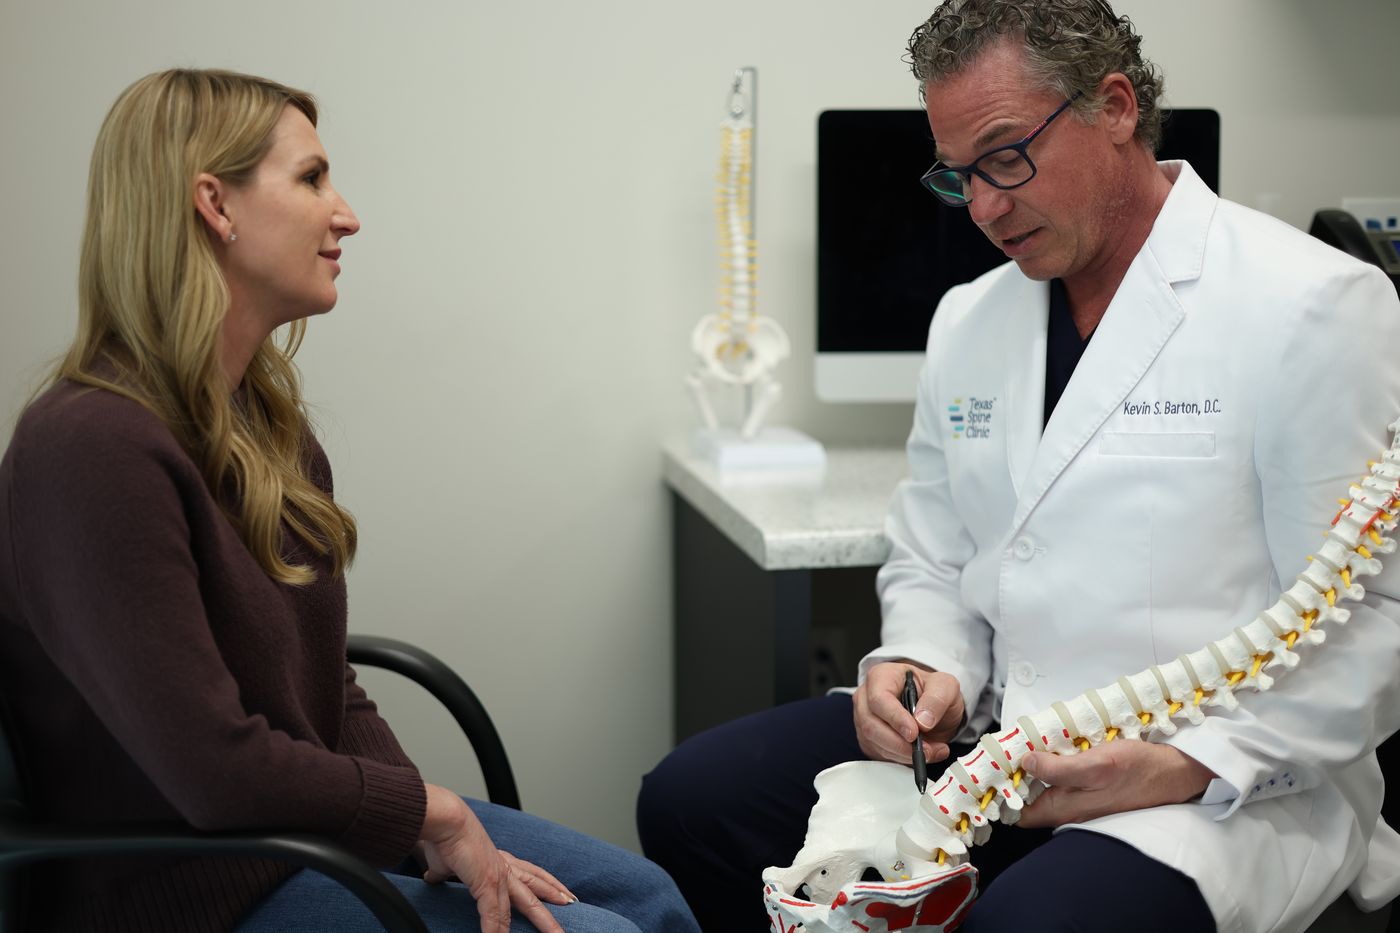
We explain it with the model in your hands, because “L5-S1 protrusion with annular fissure” means nothing until you can see the part it's describing.
Now look at your treatment history through that lens. Ibuprofen and the shot calm the
inflamed nerve. Adjustments free the joints. The sheet of exercises works the muscles. Every
one of them helps something — and not one of them changes the pressure on the disc. That's
why everything worked "for a while," and why nothing held.
Why bending is the heaviest thing your disc does —
and why the chair is a close second
Almost every herniated disc patient discovers this on their own and assumes something is
wrong with them. It isn't. It's mechanics.
Start with the part the measurements are emphatic about: bending forward loads a
lumbar disc far harder than standing upright does. Pressure has been recorded
directly inside a living disc, and lifting a weight with a rounded back registered about a
third more than lifting that same weight with bent knees — though that was measured in only a
handful of people, decades ago, and nobody is permitted to repeat the experiment
now.8 The direction isn't in question. You bend
forward dozens of times a day without counting, and for a disc that has already pushed
material backward, every one of those is the heaviest moment of its day.
Sitting is a different problem, and it's worth being exact about it, because you have
probably been told that a chair crushes your discs harder than standing does. The
measurements don't actually agree on that, and we'd rather tell you than repeat
it.9 What they do agree on is
duration. A disc behaves like a sponge under a weight: hold a load on it steadily
and it slowly gives up fluid and height, and it only takes them back when the load comes off.
An hour in a chair is a load that never lets up. On top of that, when you sit, your pelvis
rolls back and the natural curve in your lower back flattens out, so every time you reach
forward from that chair or stand up out of it you add a bending load onto a disc that has
been quietly compressing for an hour. Long and still, then flexed and loaded — that is the
pattern that provokes a symptomatic disc. Add a bumpy commute and you're doing it in a moving
vehicle.
So the desk job you went back to because "at least it isn't physical" is not the rest you
were promised. And the herniated disc patient is the one this hits hardest, because
forward-leaning load pushes disc material in exactly the direction it has already gone:
backward, toward the nerve.
This is also why you can walk a mile and feel alright, then be wrecked by a two-hour drive.
It isn't in your head, and you aren't being dramatic. Walking keeps changing the load on the
disc. The car never does.
A herniated disc is not a rest-until-it-goes-away problem. It's a load
problem. Which points at the actual treatment question: what takes the load off?
The real fear
Everybody knows somebody whose back surgery
went wrong
Maybe it was an uncle. A coworker. A friend of a friend. The back surgery that was supposed
to fix it, and didn't. They never went back to work. The pain never left. They ended up
living on painkillers, and some of them couldn't get off. They never got their life back.
You've heard those stories, and they're why you're reading this page instead of booking an
operation. That fear isn't irrational. You can have the best surgeon in the world, and back
surgery can still bring complications that can never be taken back.
"That's
why I didn't have back surgery. There were too many unknowns, and I wasn't comfortable with
that risk. If I hadn't started to improve on the DRX9000, I would have had the surgery. I
wasn't going to live with a dead foot. But I knew there was a non-surgical treatment I'd
watched work for twenty years, and its biggest risk was a few weeks of my time. So I tried
that first."
Kevin S. Barton, D.C., on his own
15 mm herniation. See his MRI.
This isn't only for people surgery turned away
Some of you were told you're not bad enough for surgery. Plenty of you are bad enough, and
a surgeon has already recommended an operation. You're exactly who should be here
first.
Frankly, it's anyone with a disc problem whose pain hasn't gotten better with the easy
stuff: the rest, the pills, the sheet of exercises, the adjustments, the shot that wore off.
Those are our patients.
Nothing is cut. Nothing is fused. Nothing is implanted. And trying this first doesn't
take surgery off the table. If you ever need an operation, every door is still
open. The one exception is an emergency: these warning signs
mean the ER today, not a consultation.
2-minute candidacy check
Is decompression right for my disc?
These are the same screening questions we ask at a real consultation.
You'll get one of three answers: worth an evaluation, worth an evaluation with a caution,
or not your answer (and what is). This is guidance, not a diagnosis.
The exam decides. Your answers stay on your device.
The mechanism
How it works — fixing the disc, not the
symptoms
Non-surgical spinal decompression takes the load off the disc itself.
The DRX9000 is an FDA-cleared, computer-controlled decompression system.
You lie on the table — clothed, fitted into a harness — for about 25 to 30 minutes. The
machine applies a slow, precise, rhythmic pull, aimed at the exact level of your
herniation, at an angle chosen for where your disc actually went.
That unloading creates negative pressure inside the disc — a vacuum effect — which draws
fluid, oxygen and nutrients back toward the disc's
center.1 The disc can rehydrate. Herniated
material can begin to retract, pulling back off the
nerve.3 At the same time the stiff joints get
motion back, the guarding muscles finally get permission to let go, and the nerve gets room
to calm down.
Most patients find it comfortable. A lot of them fall asleep.
Fully clothed. The pelvic harness goes on over your own clothes before you lie
down.About 25–30 minutes on the table. The pull is aimed at the exact level of
your herniation, at an angle chosen for where your disc actually went — set by hand, and
adjusted as you respond.
"Isn't this just traction with a fancy name?"
Same family. Different animal. Hang from a pull-up bar or lie on an inversion table and
you pull your whole spine bluntly, in one direction, with no way to target a level and no
way to control the force. Your muscles feel the yank and fight it — which is exactly the
reflex that makes plain traction disappointing.
The DRX9000 measures resistance and adjusts its pull continuously, many times a second, to
stay below the threshold that triggers that guarding reflex. It targets a
specific disc level at a specific angle. And the force curve is set by hand for your case
and changed as you respond. That control is the whole point, and it's the part home
equipment can't do.
"How do I know it will be done right?"
Ask us the hard questions — we like them. Ask whether anyone reviews your imaging before a
price exists. Ask what happens if you stop. Ask who gets turned away. The answers here are
the same every time: a doctor reviews your actual MRI before anyone discusses a plan or a
price. A disc is never diagnosed from an X-ray, because an X-ray can't show one. The exam
decides who is treated — and "no" is an answer we genuinely give. Your cost is in writing
before your program begins, and you pay only for care you receive.
"Why does it take so many visits?"
Because the disc is avascular, meaning it has no blood vessels of its own, which is why it's one of the slowest-healing structures in your body. It rehydrates the way a callus softens or a tendon remodels: slowly, with
repetition, over weeks. One session feels good and changes nothing lasting. The pressure
comes off, and then your Tuesday puts it right back on. What changes a disc is doing that
unloading again and again until the tissue itself responds.
Most programs run about 20–25 sessions over 6–8 weeks. We'd rather tell
you that now than have you find out at session four.
The doctor as the patient
Dr. Barton's own herniated disc — on camera,
imaging included
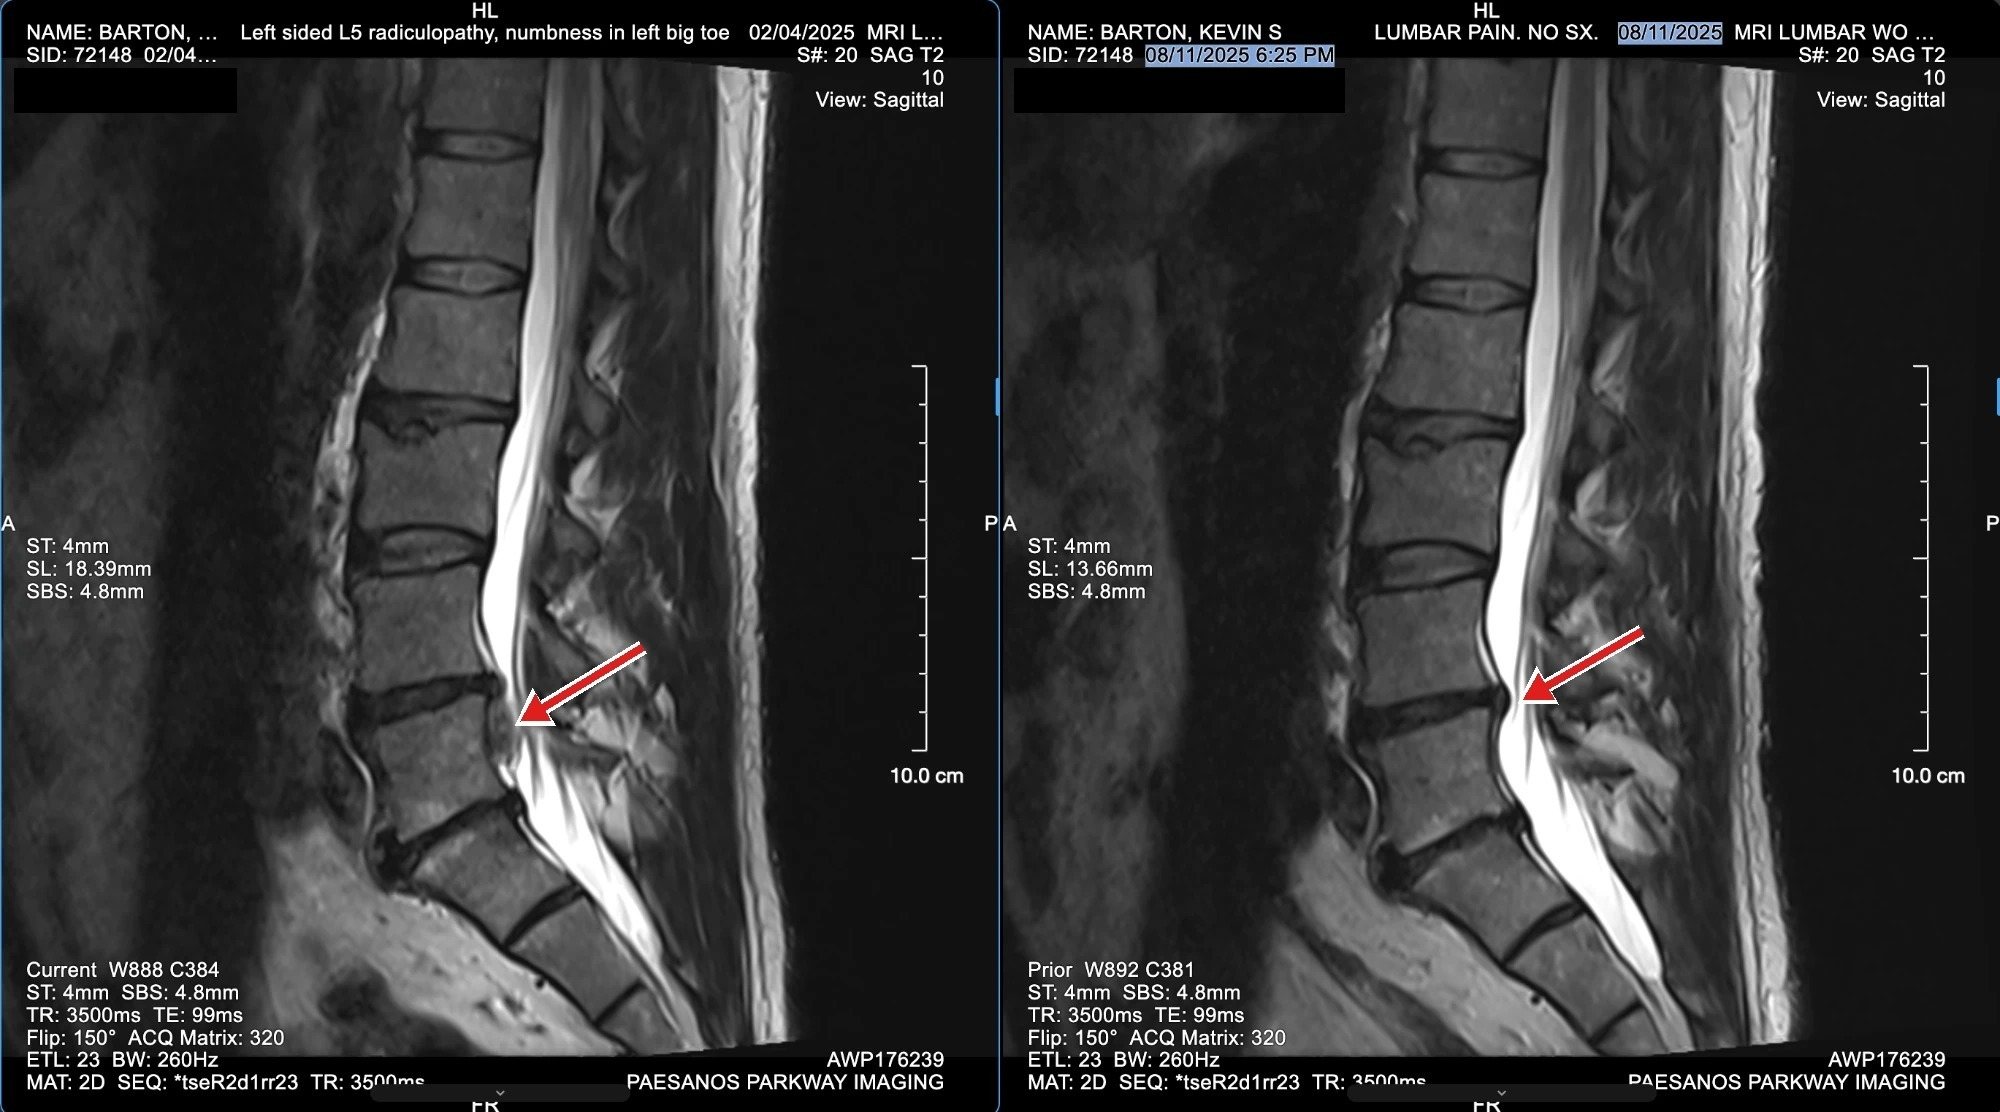
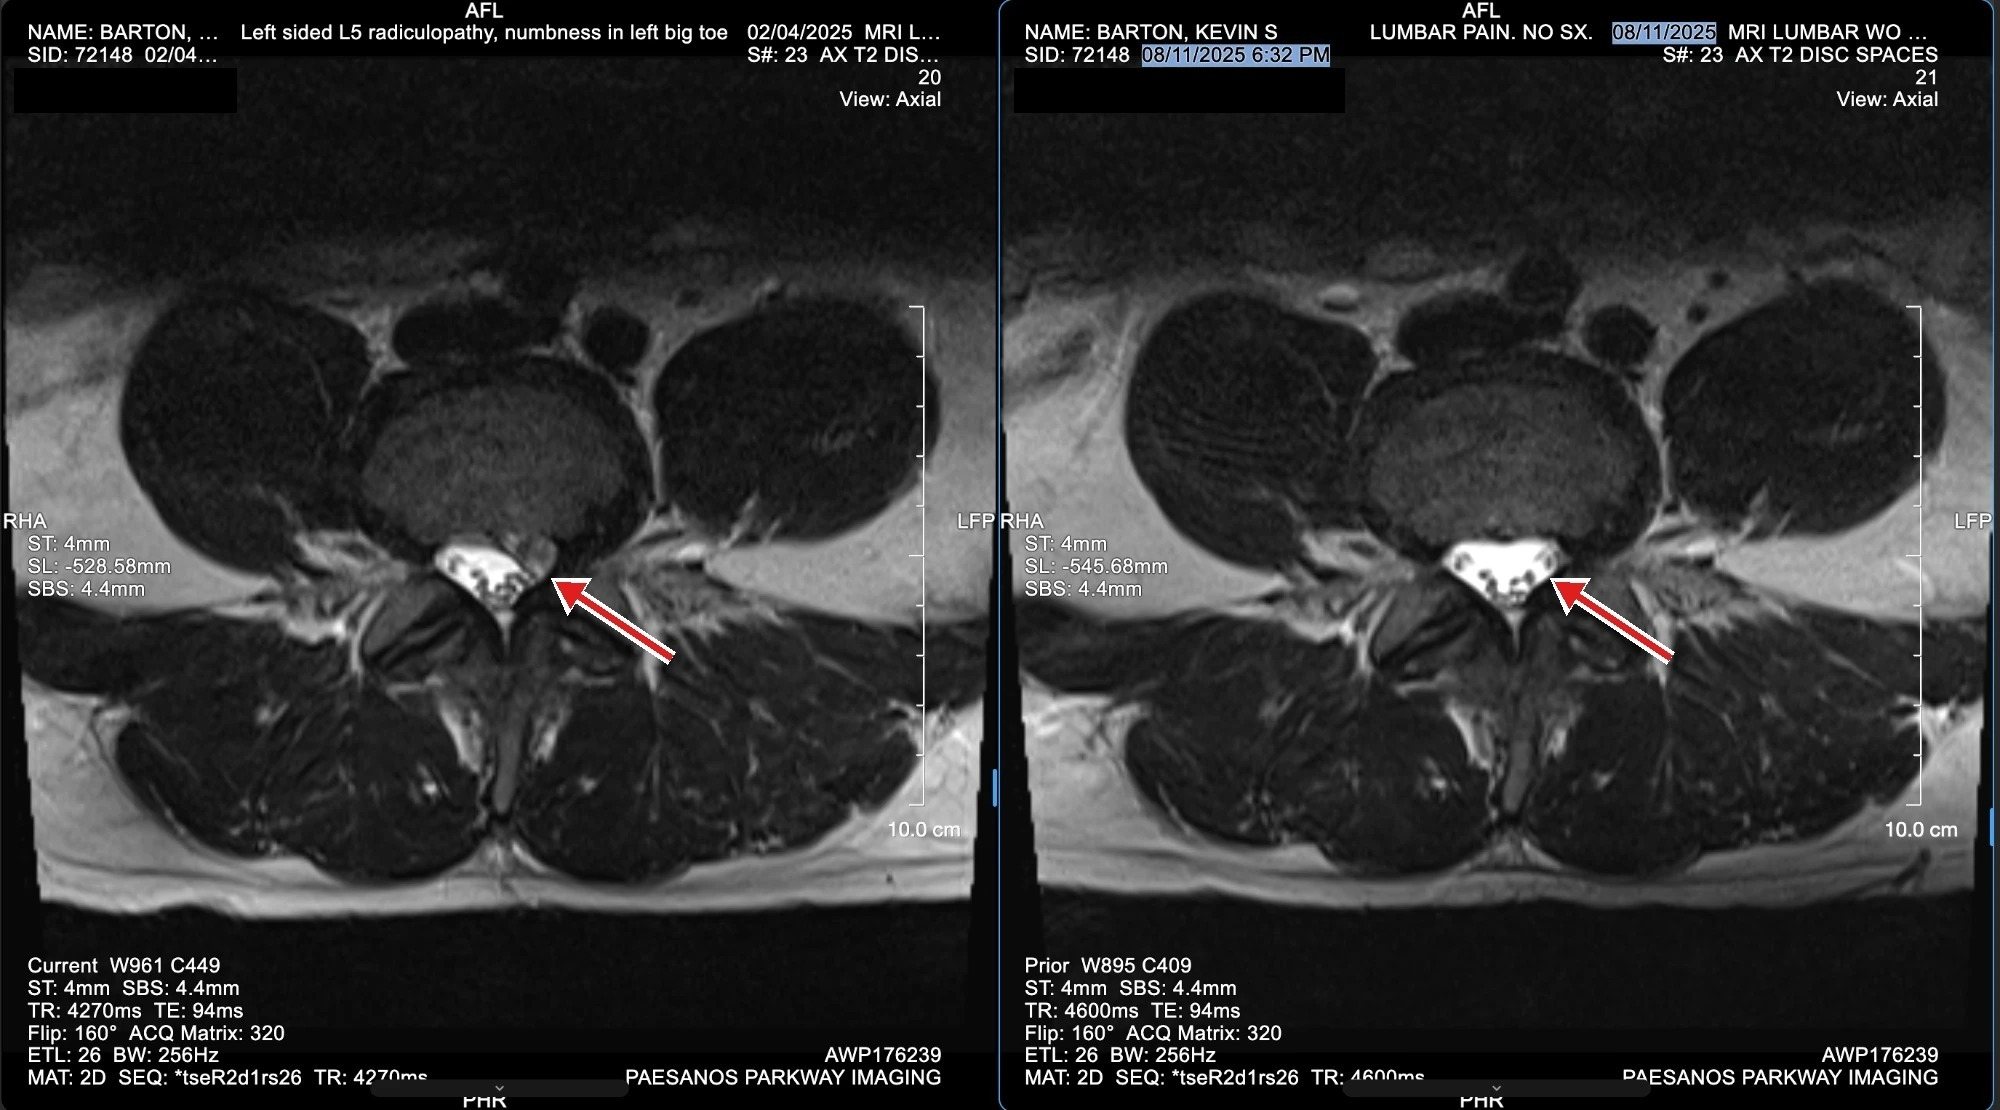
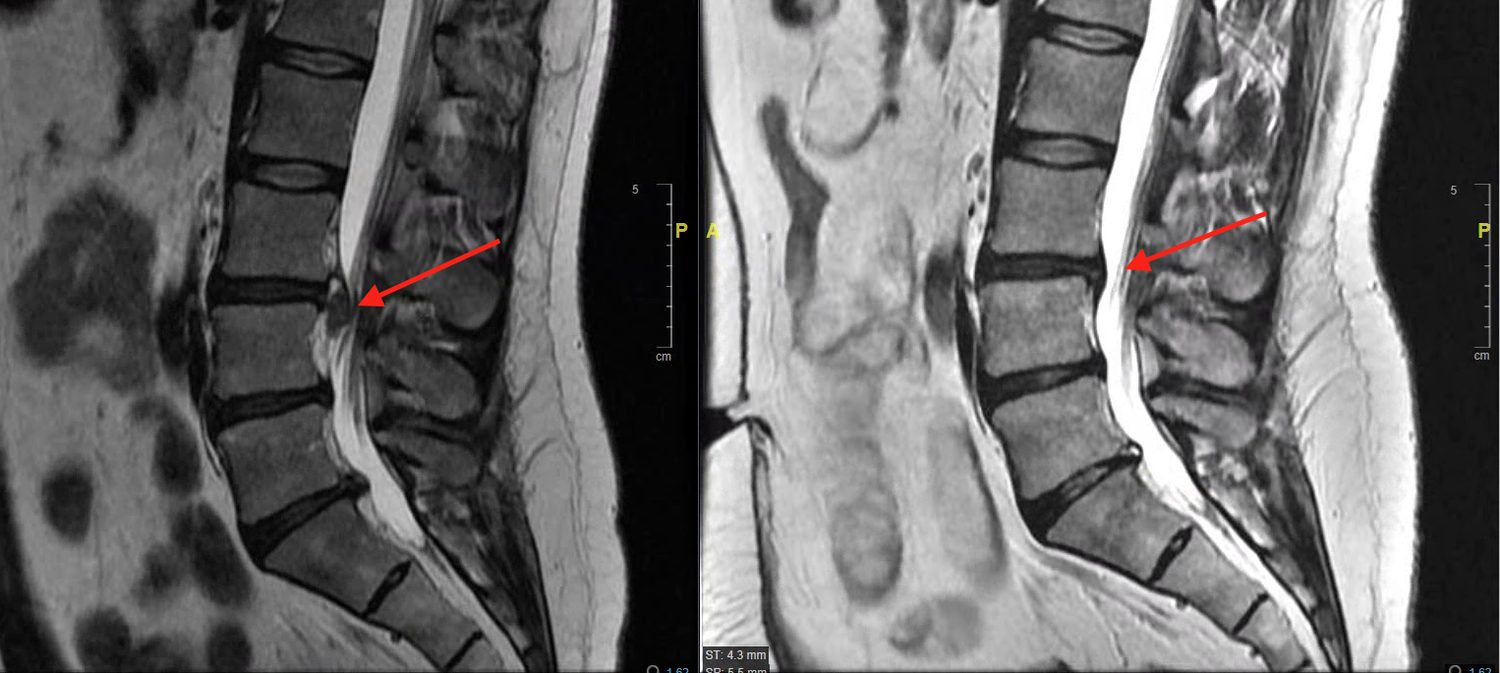
He didn't start recommending this because of a brochure. Dr. Barton's own disc herniated —
a 15 mm extrusion at L4-L5, completely compressing the descending
left L5 nerve root. One of the worst cases he had seen in over 20 years of practice, and
this time it was on his own MRI.
It came with foot drop — the L5 weakness described in the level map
above. In his words: "My big toe was completely dead, and I had no control over it at all."
In the first week of treatment he couldn't walk on his heels.
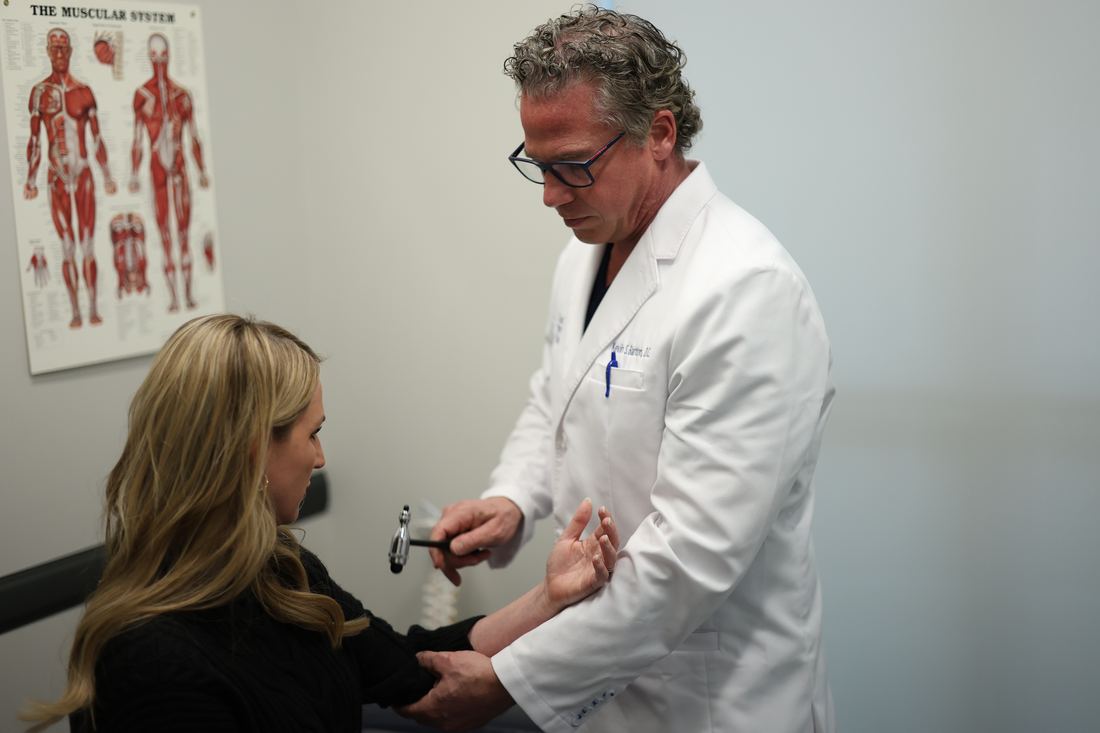
He treated it on the DRX9000 and filmed the entire course — the exam, the sessions, the
before and after MRIs. Within two weeks he had control of the big toe again; by three weeks
he could do a heel walk. The follow-up MRI shows the extrusion resolved. His own
assessment of the alternative: waiting for natural resorption "probably would have taken at
least a year, maybe longer. Meanwhile, the nerve would have been permanently damaged, and I
would have lost use of my ankle."
Why he filmed it: so you can watch what a spine doctor
with access to every option chose for his own spine, and see the result on his own MRI.
The DRX9000 page has the full series.
Whatever else you decide about this program, weigh what it asks of you. No incision.
No anesthesia. No hardware in your spine. No fusion. No narcotics and nothing to wean off. No
recovery period, and no time off work — sessions run about half an hour and you drive
yourself home afterward.
And think about what you're not risking:
No leap into the unknown. You can watch what the treatment is doing
week by week, and by week two you and we both know whether it's working.
No incision, so no surgical infection.
No scar tissue forming around the nerve after an operation.
No lying awake wondering if you've made it worse. Nothing is removed,
fused or rebuilt, so nothing here makes your spine harder to fix later.
And nothing about it closes a door. Whatever options you
have today — an injection, a surgical consult, a second opinion — you'll still have every one of
them when you're done here. That isn't true in the other direction. A fused segment doesn't come
back, and scar tissue doesn't unform. Trying the reversible thing first isn't a compromise; it's
the order that makes sense.
Why this works
Why this works — and who we won't treat
There are two reasons this program works as well as it does.
The first is the machine — and knowing how to run it. The DRX9000 is
genuinely effective at what it does, but owning one and knowing how to use it are different
things. Every protocol is set by hand: the angle of pull, the force curve, the specific level
being treated, adjusted as your spine responds week to week. We've been doing that for
21 years. That experience is the difference
between a table and a treatment.
The second matters just as much, and almost nobody in this industry will
tell you about it:
We screen patients the way a spine surgeon screens surgical
candidates.
A good surgeon doesn't operate on everyone who wants an operation. They select — carefully,
sometimes frustratingly — because the wrong patient in the wrong procedure produces a bad
outcome. We apply that standard to a table instead of an operating room.
We have turned away more patients than we can count —
including people who pushed, pleaded and offered to pay in full. Saying no costs us
money every time. It's also the only reason we've been able to do this for
21 years and still have the reputation we
have.
The exam and your imaging — not the machine, and not your credit card —
decide whether someone is treated here.
Candidacy
Who we won't put on the table
A spinal fusion or hardware at the level we'd be treating —
no exceptions
Severe osteoporosis, or a spinal fracture,
tumour or infection
Severe bony stenosis — that's a surgical conversation, and we
refer it out
Unstable spondylolisthesis — a slip that shifts more than
5 mm on the flexion-and-extension X-rays we take to check. A stable slip, of any
grade, can still be a candidate.
Two herniated-disc-specific ones worth naming here, because they're the questions this
page's readers actually have:
A sequestered free fragment.
A fragment that has fully detached can be a reason we won't treat — it
depends on your symptoms and on how big the fragment is. Depending on your exam and
imaging we may treat the level, we may watch it, or we may send you to a surgeon.
That call gets made looking at your MRI, not over the phone.
A prior discectomy.
Yes — patients who've had a discectomy or laminectomy, with no hardware left behind,
are treated here all the time. The exam and your current imaging still make the final
call, but "I've already had surgery on that disc" does not close the door.
What the early weeks are actually like
Some patients flare in the first week or two before things turn — soreness after sessions,
sometimes a temporary echo of the leg pain. That's common enough that we tell you before
you start rather than after. Patients who respond usually start noticing real change
somewhere in the middle of the program, not in the first few days. If you're getting worse
in a way that doesn't fit that pattern, we re-evaluate — we don't just keep pulling.
The exam decides. Strength, reflexes and sensation are checked
before anything is scheduled — and checked again as you go, so progress is measured
rather than assumed.
What it costs
What insurance covers, and what to expect
You'll have your figure in writing before you
commit to anything.
The decompression program isn't a covered benefit under any plan. If you carry a commercial
health plan, we can usually generate an insurance credit through it, which we apply against
your cost. How big that credit is depends on your specific benefits. So expect an
out-of-pocket investment, and expect to know exactly what it is before you commit. We verify
your benefits at no charge, paying at time of service earns a discount, and CareCredit,
Affirm and in-office payment plans are available. You only ever pay for care you
actually receive — if you paid ahead and the program stops being right for you, the
unused portion comes back to you. Cost & Insurance — how the investment
works.
What we stand behind
We don't publish a success rate — no number we could print would carry the substantiation
we'd want behind it. Here's what you get instead, and you can hold us to all of it: your MRI up on
the screen, gone through picture by picture, so you finally see what's actually wrong. An exam and
imaging that decide whether you're a candidate — not your credit card. Your number in writing
before you commit to anything. A real checkpoint at week two, where we tell you whether your
spine is responding instead of selling you another month. And your progress shown to you, not
described to you.
And we bring some mileage to that judgement. Dr. Barton has been in
practice since 2003 and has run this machine since 2005 —
21 years and more than
2,000 patients on the DRX9000. That's long enough to know which spines
respond to it and which ones don't, and to tell you which one you are early instead of
late.
The research
What it looks like in numbers
The vacuum effect was measured, not imagined. Researchers publishing in the Journal of Neurosurgery put pressure sensors inside human lumbar discs during decompression and recorded the pressure dropping to −100 to −160 mm Hg1 — a true vacuum, measured inside a living disc.
Herniations shrank more than with a sham treatment. In a randomized trial of real decompression against a sham — so patients couldn't tell which they got — the herniation index fell 27.6% with real treatment against 7.1% with sham, with better leg pain and disability scores at follow-up.3
Discs measurably gained height. Thirty patients scanned before and after a six-week DRX9000 program showed average disc height rising 7.5 mm → 8.8 mm, with pain falling 6.2 → 1.6 out of 10 — and the two changes tracked together.2
Leg pain responded most. In 73 patients compared against physiotherapy plus conventional traction, radiating leg pain and disc height improved far more with decompression.5
Across working clinics. The largest recent series followed 267 patients across multiple clinics: average pain fell from 6.9 to 2.5, with measurable improvement in reflexes and daily function.4
A vacuum measured inside the disc, discs regaining height, herniations shrinking more than sham, and leg pain responding most. Every figure here is from a named, published study. The research behind decompression.
What the change looks like on MRI
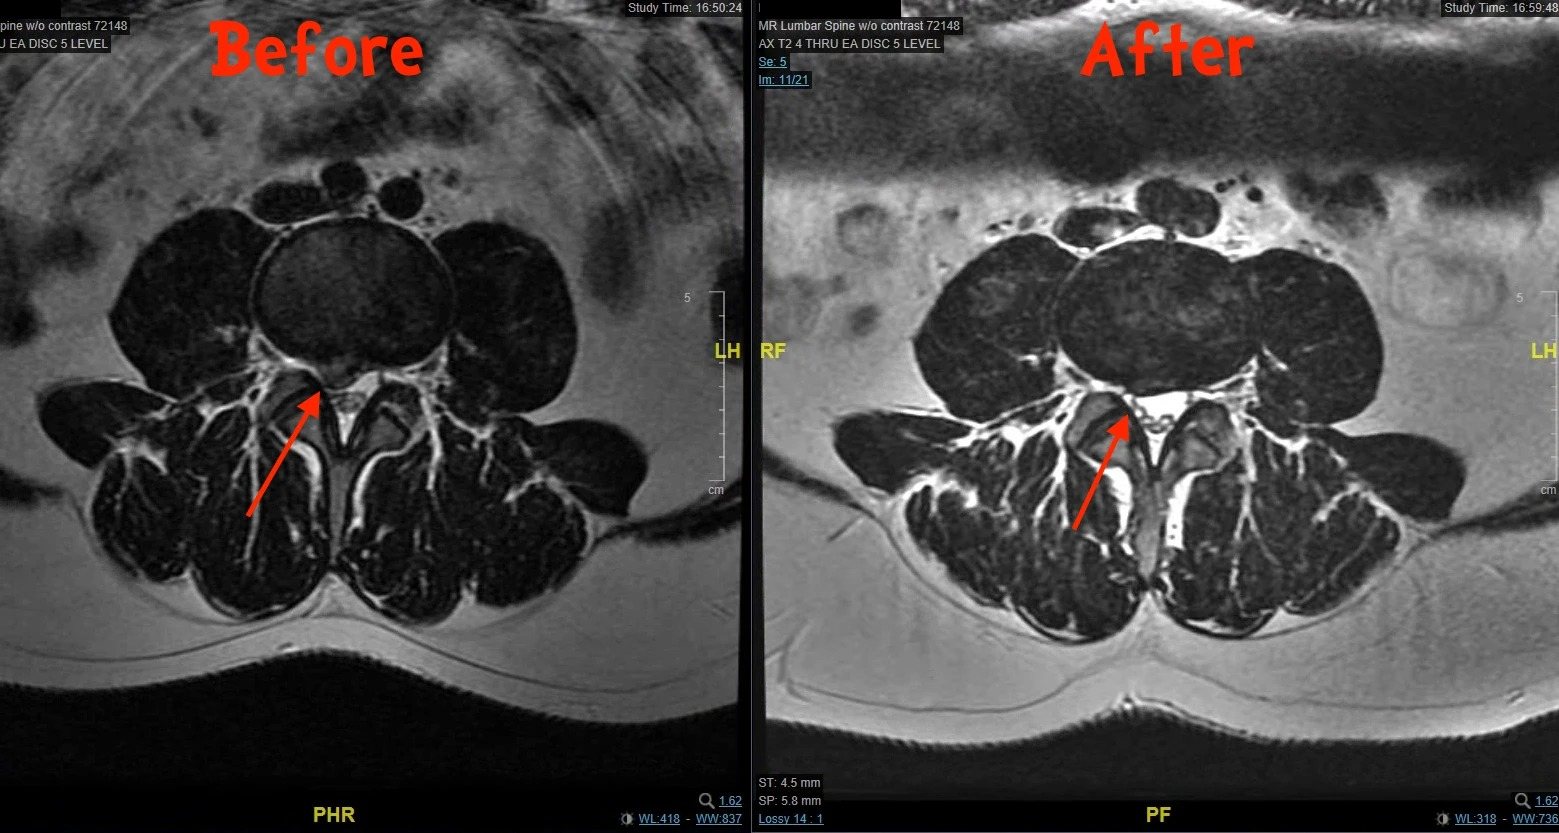
Before and after, side-on. Imaging is how disc change is measured in the
studies on this page — and how your own progress gets shown to you rather than described
to you.The same disc from above — the arrow marks the same spot on both scans, before
and after a course on the DRX9000.
Who you'll see
Your care team
We work as a team. Dr. Barton and Dr. Huffman have practiced side by side for
more than 18 years, and your care is a team effort from your first visit.
Kevin S. Barton, D.C.
Chiropractor · In practice since 2003
Dr. Barton has been in practice since 2003 and has used the DRX9000 since 2005, with more
than 2,000 patients treated on it. He's the author of the treatment philosophy here: find
the source of the pain and treat it there, without surgery and without narcotics. He
completed advanced scrambler therapy training in Rome with Dr. Giuseppe Marineo, the
inventor of the treatment.
In 2025 he went through the DRX9000 program himself, for one of the worst herniated discs he'd
seen in his career, and filmed the whole course of treatment, MRIs included.
Watch his nine-part series.
Joshua C. Huffman, D.C.
Chiropractor · In practice since 2007
Dr. Huffman earned his Doctor of Chiropractic degree from Texas Chiropractic College in
Pasadena, Texas, and completed his internship at Moody Health Center, with a rotation at
the Michael E. DeBakey VA Medical Center in Houston. He has advanced training in
myofascial release technique and is certified as a designated doctor for the State of
Texas.
A Texas native, he was born and raised in Matagorda County. When he isn't getting
patients well, he's hunting, fishing, kayaking and hiking with his wife, Kendra, and their
two children, Titus and Alley.
How the program runs
Decompression and strengthening, together
It isn't two programs, and the strengthening doesn't wait until the end.
Taking pressure off a disc gives it a chance to recover. It doesn't rebuild what got you
here. So alongside decompression, from as early as your symptoms allow, comes core
strengthening and therapy that rebuild the support around the disc — the muscles that hold your spine's
position when you're tired, driving, lifting a kid, sitting through a meeting. Dr. Barton
calls it your structural margin. It's the difference between finishing the
program out of pain and finishing it hard to hurt again.
Along the way you get re-examined on a schedule — not asked to take
progress on faith. Reflexes, strength, range, what your leg is doing. You'll see your own
numbers move, or not move, and we'll say which out loud.
And after the program ends: what comes next is the
aftercare that protects the margin you just spent eight weeks building. A handful of
things to keep doing — how you sit, how you lift, what to do at the first sign of a bad
week — and periodic maintenance treatments that take the pressure off the disc from time
to time. A disc feeds by exactly that pressure exchange, and ordinary life never stops
loading it. We'll recommend the schedule that fits your case, and tell you why.
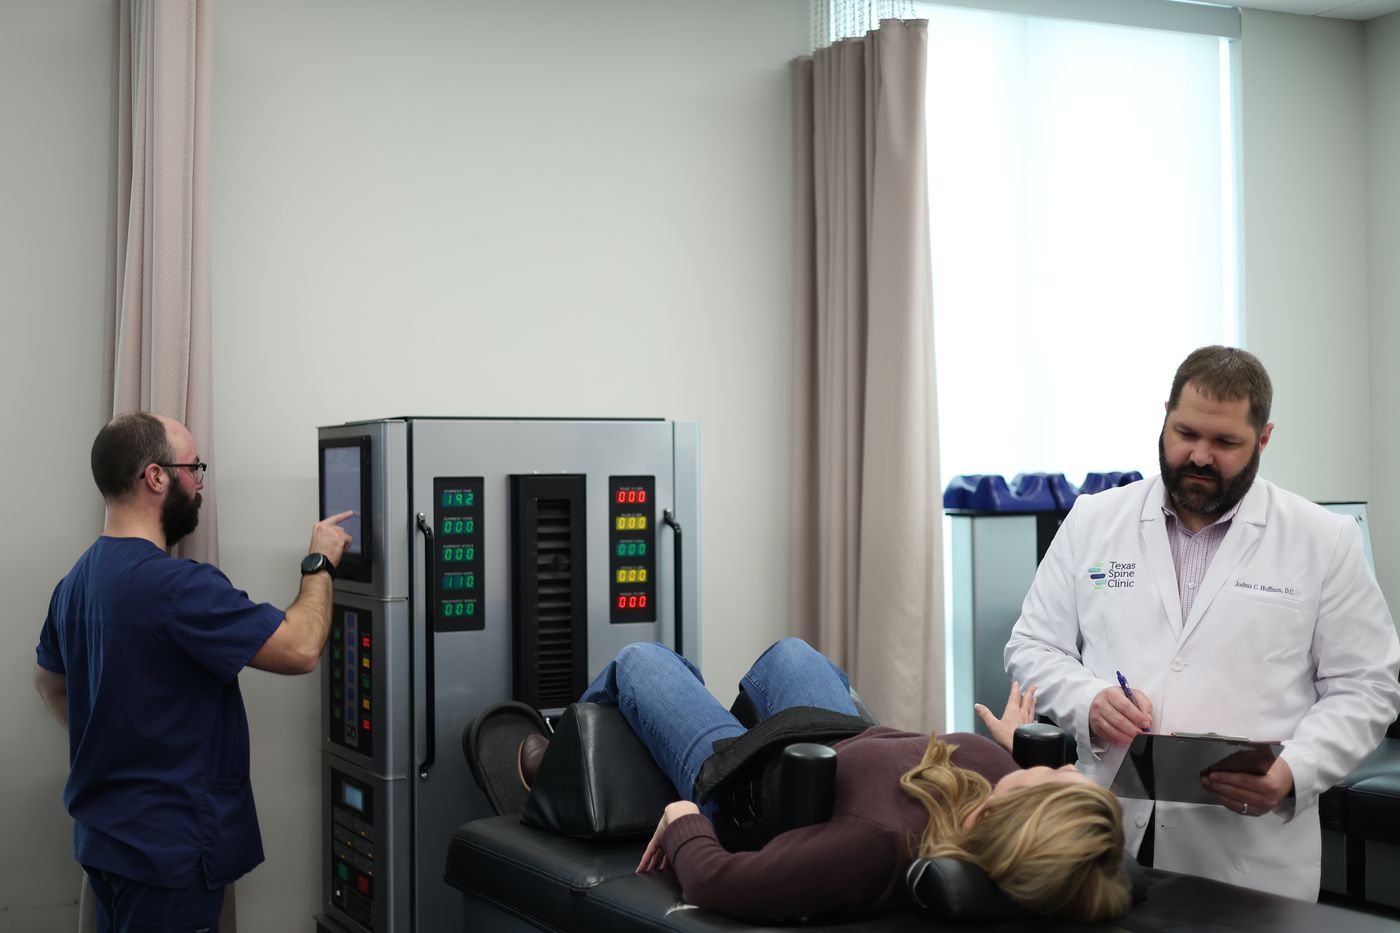
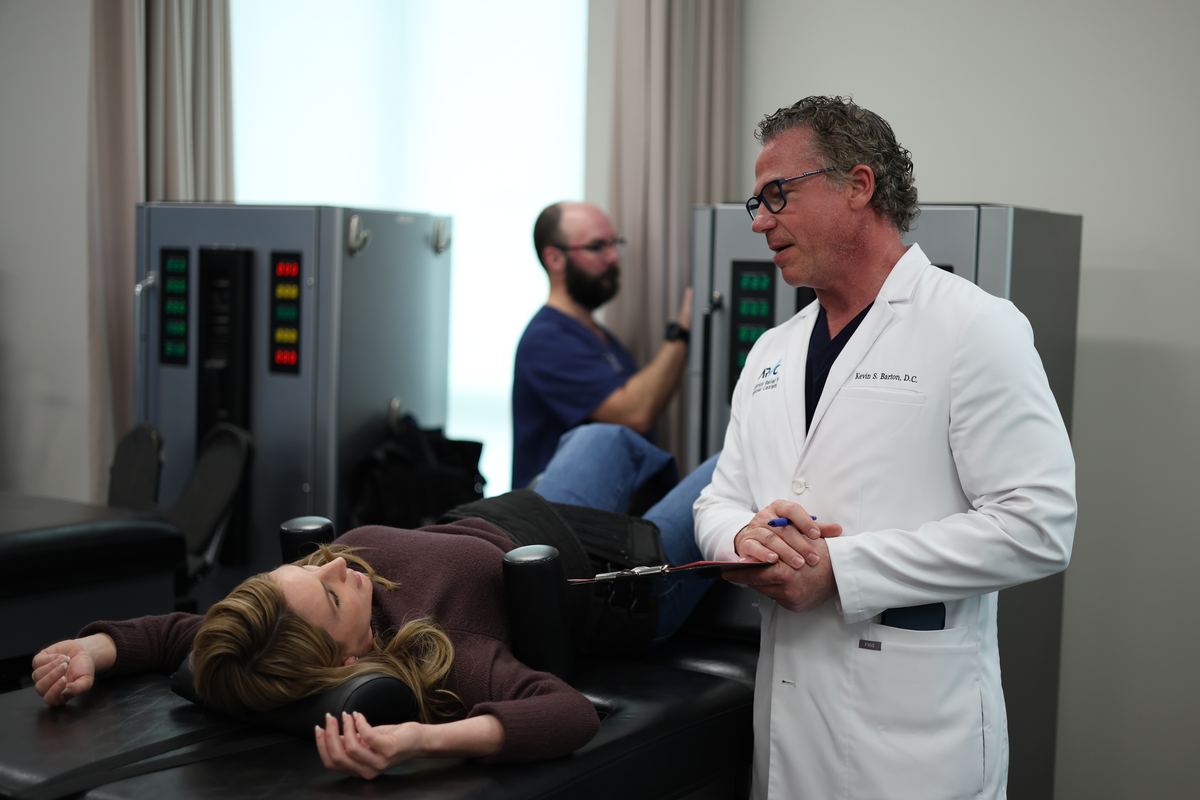
The DRX9000 room. Taking the pressure off the disc, session
by session.The therapy room. Rebuilding the support around the disc,
running alongside decompression — not after it.
“I am so grateful to Dr. Huffman and Texas Spine Clinic for offering
Non-Surgical Spinal Decompression treatment. After a few short series of treatments, I
always leave pain-free… The team, the physical therapists and Jennifer (the
receptionist), are so attentive and caring.”
Katie Breedlove★★★★★ · Posted on Google
“When I started the program, I was in pain all day and had trouble sleeping at
night due to pain. I was using a walker at home and struggled with a cane when I went to
the doctor. I was confined at home with pain killers. Now, I don’t take pain
medication… I have made so much progress, and my activity level has improved
greatly.”
Betty Cisnero★★★★★ · Posted on Google
“Dr. [Huffman] and his Physical Therapists have been dedicated in healing my
back and sciatica problems. I appreciate all that they have done in helping my relieve
my pain and suffering They communicate well and I can’t say enough how they have helped
my healing process.”
Alfred Hawkins★★★★★ · Posted on Google
Reviews quoted verbatim from our
public Google profile.
Individual results vary. These are real Texas Spine
Clinic patients who consented to share their stories — watch them tell it in their own
words.
Questions patients actually ask
Before you call
Can a herniated disc really shrink without surgery?
Some do. Herniated material can be broken down and reabsorbed by the
body over months, and in the one sham-controlled trial in this field, herniations shrank
measurably more with real decompression than with a fake version of
it.3 That's why we re-examine on a schedule and
show you your progress, and why we make the keep-going-or-stop call around week
two.
My MRI says "degenerative changes" and I'm 34. Is my spine falling apart?
No. Radiologists compare every spine to a young textbook one, and
anything less gets called degenerative. It means your disc has lost some water and height
under load. Plenty of people in their twenties and thirties who have never had back pain
have the same words on their reports. It describes mileage, not a countdown.
Degenerative disc disease — the full explanation.
My surgeon said wait until it's worse. Is that wrong?
It's not wrong — it's surgical logic, and it's sound. Surgery
carries real risk, so surgeons hold it back until the scale genuinely tips. The problem
is what's missing from that plan: anything to do in the meantime except pills and time.
That gap is exactly what this program is for. And if you do end up needing surgery
someday, arriving stronger and less inflamed costs you nothing.
I'm terrified of ending up fused. Is that where this is heading?
Probably not, and it's worth separating two very different
operations. Most surgery for a straightforward herniated disc is a
microdiscectomy — the surgeon removes the piece pressing on the nerve.
Nothing gets fused. Fusion is a much bigger operation that locks two
bones together, and it's usually proposed for instability or multi-level problems, not
for one herniated disc. The "back surgery never works" stories everyone has heard are
generally about the bigger operations, or about people whose pain was never coming from
where the surgery went. If someone has proposed a fusion to you, that is absolutely a
second-opinion conversation — and it's one we'll have with you including when
the answer is that you should go talk to a surgeon.
I already had a discectomy and it came back. Why?
Because the operation removed the fragment, not the load. The shell
of the disc still has a weak spot, and your Tuesday is unchanged — same chair, same
commute, same lifting, same guarding muscles. Re-herniation is uncommon, but it's common
enough that surgeons discuss it with you beforehand. And here's the answer to the
question you're really asking: yes, we treat patients after a discectomy — routinely, as
long as no hardware was left behind. The exam and your current imaging make the final
call, so bring the operative report along with the MRI.
What about the numbness in my foot?
Take it seriously. Pain means a nerve is irritated. Numbness and weakness
mean the nerve is being squeezed hard enough to stop doing its job — and
that's a different clock. Often it recovers as pressure comes off. But a nerve that's
been compressed hard for a long time recovers more slowly, and sometimes not
completely. Trouble lifting the front of your foot, a leg that gives way, or numbness
that's spreading are the best reasons on this page not to park this problem for
another year.
New loss of bladder or bowel control,
rapidly worsening weakness, or numbness in the groin, the inner thighs, or the area
you sit on — what doctors call saddle anesthesia → emergency room today, not an
appointment.
Why does sitting hurt so much more than walking?
Not because a chair presses harder on the disc than standing does —
that gets repeated everywhere and the measurements don't support it. It's that a chair
holds the load still. A disc under a steady load slowly gives up fluid and
height, and only takes them back when the load comes off. Your pelvis also rolls back
and the curve in your low back flattens, so every reach forward and every stand-up adds
a bending load — and bending genuinely is the heaviest thing a disc does, pushing
material in the same direction it has already gone. Walking keeps changing the load. The
chair and the car never do. It's mechanics, not weakness.
Can I just use an inversion table at home?
You can, and some people get temporary relief from one. What it
can't do is target the level, control the force, or stay below the threshold where your
muscles fight the pull — it's a blunt, whole-spine stretch with no measurement behind
it. If home traction had solved herniated discs, this clinic wouldn't exist. If it's
helping you and you're comfortable on it, keep using it. Just don't confuse it with a
treatment protocol.
Is my disc going to keep getting worse?
Not on a fixed schedule — that's the part the word "degenerative"
gets wrong. But a disc that stays compressed keeps losing water and height, and the
tissues around it keep compensating. The realistic goal isn't to freeze time. It's to
change the loading story: take the pressure off, let the disc recover what it can, then
strengthen the support around it so you're not back here next year.
Footnotes
Ramos G, Martin W. Effects of vertebral axial decompression on intradiscal
pressure. J Neurosurgery 1994.
↩
Apfel CC et al. Restoration of disk height through non-surgical spinal
decompression is associated with decreased discogenic low back pain.
BMC Musculoskeletal Disorders 2010.
↩
Choi E et al. Effectiveness of non-surgical spinal decompression vs sham —
randomized controlled trial. Int J Clinical Practice 2022.
↩
Schueren M et al. Military Medicine 2025 — 267 patients across 7
clinics. ↩
El-Zayat M et al. Egyptian Rheumatology & Rehabilitation 2019 —
decompression vs. physiotherapy with traction.
↩
Brinjikji W et al. Systematic literature review of imaging features of spinal
degeneration in asymptomatic populations. AJNR Am J Neuroradiol
2015;36(4):811–816. ↩
Brinjikji W et al. MRI findings of disc degeneration are more prevalent in
adults with low back pain than in asymptomatic controls. AJNR Am J Neuroradiol
2015;36(12):2394–2399. ↩
Wilke HJ et al. New in vivo measurements of pressures in the intervertebral
disc in daily life. Spine 1999;24(8):755–762.
↩
Li JQ et al. Comparison of in vivo intradiscal pressure between sitting and
standing: a systematic review and meta-analysis. Life (Basel) 2022;12(3):457.
↩
Call (210) 741-9166 or send the
form. The consultation is $49 — it covers the examination, the review of
your imaging, and, if the exam and imaging say you're a candidate, your first
treatment.
Here's exactly what happens:
You call or send the form, and we schedule your consultation.
Bring your imaging — the disc, the report, or both. If you don't have an MRI yet, we'll
talk through how to get one. Nobody quotes you a price before someone has looked at your
spine.
The doctor examines you, then puts your MRI on the screen and goes
through the pictures with you — not just the report. The millimetres. The
direction it went. The impingement. The "degenerative" line, on your own scan. For a
lot of our patients this is the first time anyone has actually done that.
You get one of three straight answers: you're a good candidate,
you're not, or here's the option that fits you better — plus your real cost in writing
with your insurance credit already calculated. Two of those three answers earn us
nothing. We give them out constantly.
You'll leave understanding your own spine either way. That's the deal.
P.S.
Right now that report is a source of dread. It sits in a folder or an email you don't open,
full of words that sound like a verdict. Here's what it actually is: the hardest diagnostic
part, already done. You have the picture. Most people never get further than being
frightened of it. One consultation turns it into a plan — and if the plan shouldn't be us,
we'll tell you that, out loud, and you'll still walk out understanding your own spine for
the first time.