

For amputees whose phantom pain hasn't let up — and the people who love them
The limb is gone. The pain in it isn't.Here's a way to go after the signal — no pills, nothing implanted.
Phantom limb pain is real, and it comes from nerves that are still very much there. Scrambler therapy is an FDA-cleared, non-drug treatment that sends a different message up those same nerves. Small pads go on healthy skin. No needles. No medication. Nothing implanted. Nothing to recover from. And a $99 first session tells you early whether your body is answering it.
Somebody probably told you it would fade. Six months, maybe a year, and your brain would catch up with the rest of you.
It didn't. Or it held off for months, and then one night it arrived all at once.
And it isn't "leg pain." It's your toes being cut. It's an ankle that feels freshly broken for ten minutes straight, no matter what you do. It's a hand gripping something burning that it can't let go of, or fingertips caught in a pair of pliers. It's lightning through a foot you haven't had in years.
It knows what time it is, too. Two in the morning. Three. The house is quiet, there's nothing to distract you, and the phantom gets loud. You wait until you're too tired to feel it. You get three hours. Then you get up and do it again.
You have a list. Gabapentin — maybe a big dose, four times a day — and the fog that came with it. Pregabalin. Duloxetine. Baclofen. Medications that worked for a while, until your body got used to them and the pain came back through. Maybe opioids, and everything that came with those. A TENS unit from the internet. Mirror therapy at home, on your own, just in case.
And there's a quieter wound: having to explain that it's real. That a foot you don't have can hurt. You've seen the look. Maybe you've stopped bringing it up.
If you're the husband, the wife, the son or the daughter reading this — you've asked how you can help, and heard "nothing, really." This page is for you, too.
Here's the part that matters: the pain is real because the nerves are real. The limb is gone. The nerves that served it are still there, and so is the part of your spinal cord and brain that listened to them. Phantom limb pain is a signal problem — and a signal is something that can be worked on.
If nobody has offered you scrambler therapy, there's a simple reason: insurance rarely covers it, so very few clinics own the machine, and it's new to most doctors. There is one in San Antonio.
First, the distinction that matters
Three different things — and which one this page is for
If you've lived with limb loss for any length of time, you already know these aren't the same. They aren't treated the same, either.
Phantom limb pain — this page is about this one.
Pain you feel in the part that's gone. Burning, stabbing, crushing, cramping, electric. The toes, the heel, the fingers, the palm. It can be constant or come in attacks, and it's often worst at night. This is the pain scrambler therapy goes after.
Phantom sensation — normal, and nothing to fix.
Feeling that the limb is still there without it hurting. Knowing where your foot is. Being able to "wiggle" toes that aren't there. It's a normal part of limb loss, many people have it for life, and it doesn't need treatment. If it doesn't hurt, you don't need us for it.
Residual-limb pain — see your prosthetist and surgeon first.
Pain in the limb you still have (the stump, as a lot of people call it): the skin, the end of the bone, the fit of the socket, or a sensitive nerve ending at the cut, called a neuroma. Those have physical causes, and the people to check them first are your prosthetist and your surgeon. If they've looked, and what's left is nerve pain, bring that to the consultation and we'll tell you whether this fits.
Plenty of people have more than one of these at once. That's fine. Sorting out which is which is the first thing the consultation does, so the right thing gets treated.
The mechanism
How it works — in plain words
Start with where phantom pain comes from.
When a limb is lost, the nerves that served it are cut — but they don't go silent. They still run up to your spinal cord, and your brain still keeps its map of the hand or the foot. Sometimes that circuit starts sending pain, and keeps sending it, whether there's anything at the end of the line or not. The alarm is going off in an empty room.
That's why the usual tools struggle here. A pill that lowers the volume doesn't change the message. It quiets the signal for a while, then your body adjusts, the dose climbs, and the pain comes back through.
Scrambler therapy goes after the message.
Small adhesive electrodes — the kind used for an EKG — go on healthy skin with normal feeling, on the nerve pathways that serve the area that hurts.2 Never on broken, irritated or numb skin. The whole idea depends on nerves that still work well enough to carry a signal.
The machine then sends its own signal up those nerves. It isn't a buzz and it isn't random. The device builds sequences of waveforms, changing constantly, shaped to imitate the traffic a healthy nerve sends when nothing is wrong.2 Your nervous system gets a non-pain message on the same line that has been carrying pain — over and over, for about forty minutes.
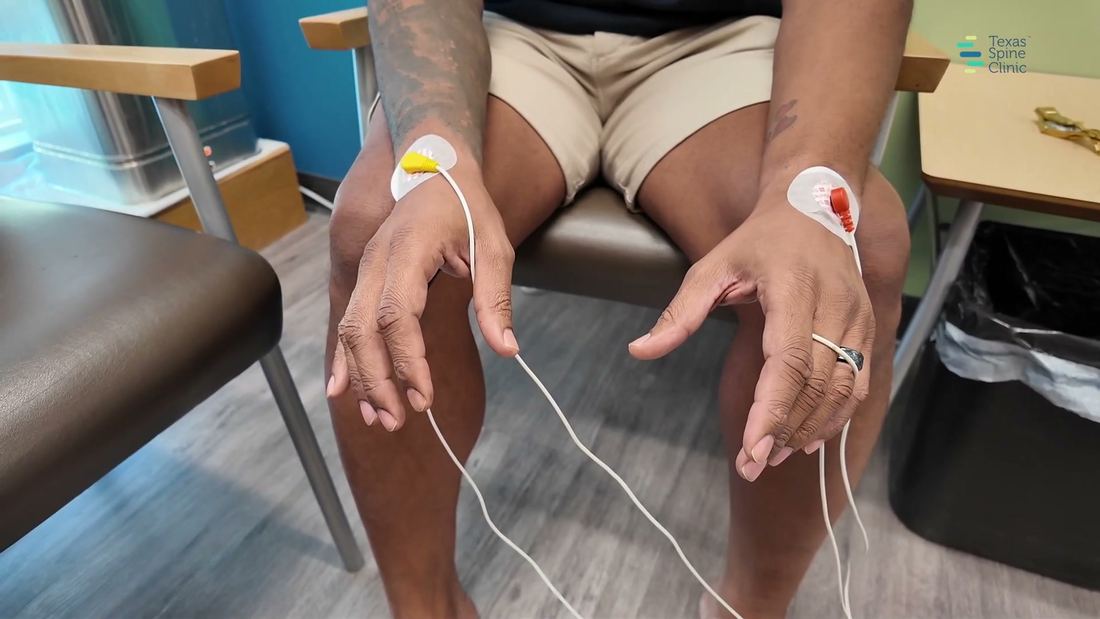
During the session, the target is your pain at zero, or as close as your body will go that day. Then you go home, and the question becomes how long it holds. For people who respond, relief tends to last a little longer after each session over the course.2
The questions everyone asks
"How can you treat a limb that isn't there?"
We don't treat the limb. We treat the signal. The pain is coming from nerves you still have — and those nerves are what the pads talk to.
"Isn't this just a TENS unit?"
No. Same kind of sticker, different treatment — the New England Journal of Medicine review is explicit that scrambler therapy is not a version of TENS.2 A TENS unit is set by you, at home, and works while it's on. The scrambler's signal comes from the device's own program, it's given as a course aimed at relief that outlasts the session, and it's restricted to physicians and trained staff under a physician's supervision.3 If a TENS unit did nothing for your phantom pain, that tells you nothing about this.
"Does it hurt?"
It shouldn't, ever. A properly run session feels like a comfortable tingle. If anything we do makes the pain go up, we stop and change something. That's the instruction that comes with the machine,3 and it's how we run it here.
Phantom limb pain, specifically
How we run it for phantom pain
Phantom pain has a few questions nobody else asks. Here are the straight answers.
Where the pads go, when the part that hurts is missing.
It's the first thing most amputees ask, and it's a good question. The rule is the same for everyone: the pads go on healthy skin with normal feeling, just outside the area that hurts, on the nerve pathways that served it — never on skin that is broken, irritated or numb.3 For a phantom limb, that means working out the placement on the body you have, by hand, at your first session, with you telling us what you feel — and moving the pads until the pain answers. If the skin on your residual limb is sore from the socket, we place around it.
Mirror therapy, during treatment.
Mirror therapy was first developed for phantom limbs.5 A mirror is set up so your intact limb's reflection sits where the missing one would be, and your brain gets to watch a limb that moves normally and doesn't hurt. You may have tried it at home. Here, when phantom pain is stubborn against the scrambler sessions alone, we use it during treatment — while the pain is already down — so the brain gets a better picture to work with than it has had in a long time.
Someone with you, the whole session.
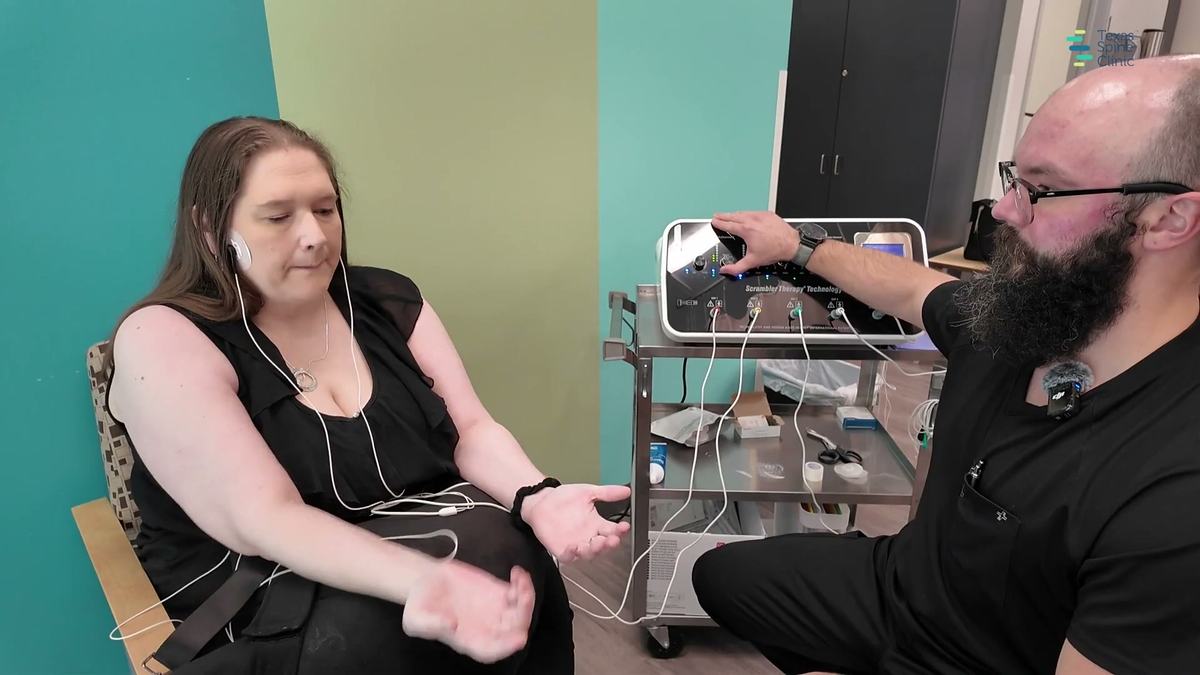
We don't put the pads on and walk away. Someone stays with you, keeps checking what the phantom is doing, and changes the setup on the spot if the pain isn't answering.
A protocol that keeps changing until it gets the answer.
Placement, level, sequence, what we add and when — we vary the approach across the course instead of repeating one setup ten times. The target every session is your phantom pain at zero while you're in the chair.
All of it is part of the protocol. The mirror work and the rest of what we built for stubborn nerve pain aren't add-ons, and they aren't billed on top of anything.

If you lost a limb in service
San Antonio is Military City, and some of the people reading this page lost a limb in uniform. You may have lived with phantom pain for ten or twenty years. You've been through the pain clinics and the medication changes, and you're still looking. This is worth an hour. Texas Spine Clinic is a private practice, and you don't need a referral from anyone to come see us.
If you're weighing an implant or another surgery for the pain: nothing here is implanted, nothing is cut, and nothing here closes a door. It's the kind of thing worth finding out about first.
What to expect
What a session is like — and what the course looks like
You sit or lie back in a treatment room. No gown, no straps, nothing to climb into.
The pads are placed by hand. Then the level comes up slowly, one channel at a time, and here is the only thing you have to do: tell us what you feel. First tell me when you feel something, then tell me when it's enough.2 The target is a clear, comfortable tingle — in the phrase the published description uses, like being bitten by tiny electrical ants.2
The session runs about forty minutes.3 People read, scroll, nap, talk. When it ends, the pads come off and you drive yourself home. Nothing to recover from, no drowsiness, no restrictions.
A full course is ten sessions, on consecutive weekdays — five days a week for two weeks.3 That's why we run scrambler sessions on Fridays, when the rest of the clinic is closed. If you're driving in from out of town, plan on two weeks in San Antonio.
But you don't decide about ten days on day one. Here's how it actually goes:
- First, a $19 consultation. About an hour, Monday through Thursday: roughly thirty minutes of history and examination, then about thirty minutes of treatment. We sort out which pain is which, go over what you've tried, and check you against the list of reasons someone can't have this treatment.
- Then a $99 first session — credited toward the course. A full session, run properly, so you can see what your own nerves do with it before you commit to anything.
- Then you decide. If there's a signal, we talk about the full course, and you'll have your number in writing before you commit. If there's nothing, we say so, and we stop.
For people who respond, relief usually builds over the course rather than arriving all at once. Some people's pain comes back in time, and they respond again to a short round of booster sessions — usually a couple of days, not another full course.2 In San Antonio, a booster is a drive, not a flight.


Why this works
Why this works — and what we stand behind
Scrambler therapy retrains the pain signal instead of masking it. Here's what makes it work here, and what you can hold us to.
It works on the signal — which is where phantom pain lives. Not on the limb that's gone, and not by turning down the volume on everything else in your head.
Who runs it matters. Everything depends on where the pads go and whether the level is set by someone paying attention to your answers. Dr. Barton trained in the protocol in Rome with the inventor, Giuseppe Marineo — and every course here runs under the medical supervision of Lisa D. Persyn, M.D.
Stubborn pain gets more than the machine. Mirror therapy during treatment, a protocol that changes until the pain answers, and someone with you the whole session.
What we stand behind
A full session before you invest in a course. Your number in writing before you commit to anything. Progress measured the same way every time — how bad the pain gets, how often it comes, and what you can do again, like sleeping through the night — with standard questionnaires at your first visit and at every re-check. We listen to our patients and never ignore what they tell us. And if it isn't working, we tell you, and we stop.
Candidacy
Who this is for — and who we won't treat
Who this is for
- Phantom limb pain after an amputation — arm or leg, recent or decades old
- Pain that has outlasted the medications, or that the medications only turn down
- Anyone who wants to try something non-invasive, with nothing implanted, before anything more drastic
- Other nerve pain, too — CRPS, shingles pain, and neuropathy — see the full scrambler therapy page
Who cannot have this treatment
These are absolute. They come from the device's own instructions, and no exam changes them:3
- An implanted pacemaker or defibrillator
- A spinal cord stimulator or peripheral nerve stimulator, implanted or in trial
- Aneurysm clips, vena cava clips, or skull plates
- A seizure disorder — epilepsy, or a tendency to seizures
- Pregnancy — the treatment hasn't been studied in pregnancy, so it isn't used
- Undiagnosed pain — pain nobody has worked up yet needs a diagnosis first, not a treatment. If that's where you are, we'll help you get to the right person.
Where we take extra care
Heart problems, diagnosed or suspected — we talk to you about it, and there are placements we don't use. Skin that has lost normal sensation, or is broken, infected or fragile where pads would go. A tendency to bleed or bruise easily, or a recent fracture. Some anticonvulsant medications can change how the course is run — bring your full medication list to the consultation. And occasionally, skin irritation where the pads sit: it's the most common side effect there is, and moving the placement usually solves it.3
Cost & insurance
What it costs — and what you get for it
The consultation is $19.
History, examination, sorting out which pain is which, and the candidacy screen above. If the answer is no, you hear it at the consultation.
A first full session is $99 — and it counts toward the course.
Not a demo — a full session, run properly, so you can find out what your nerves do with this treatment before you're asked to commit. Continue with a course and the $99 comes off it.
The full course is an investment we quote in person.
Scrambler therapy isn't a covered insurance benefit, so the course is an out-of-pocket investment — and you'll know exactly what it is, in writing, before you agree to anything. You only ever pay for care you actually receive.
Your care team
Who does the treatment
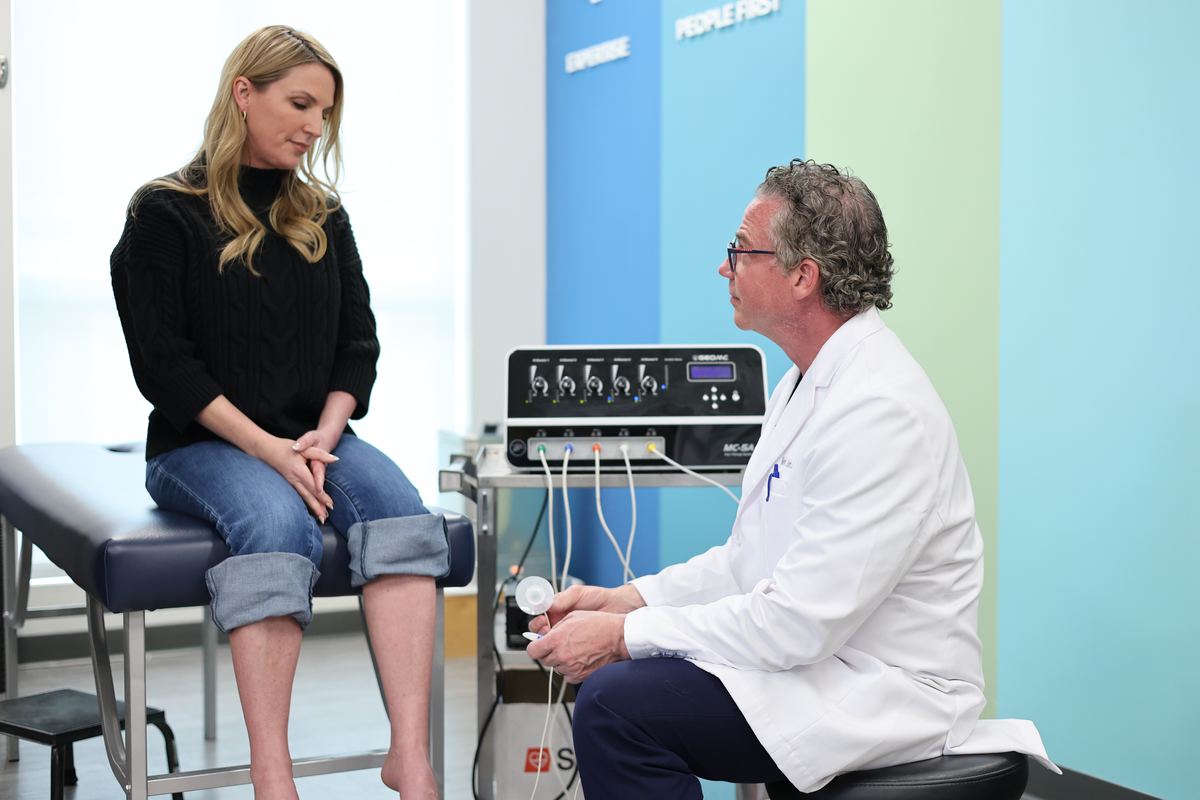
With scrambler therapy, who is placing the pads matters as much as the machine. For a phantom limb, where every placement is worked out on the body you have, that's doubly true.
Kevin S. Barton, D.C. has practiced in San Antonio since 2003. He manages the scrambler program, and he does the treatments.
He completed advanced scrambler therapy training in Rome, Italy, with Dr. Giuseppe Marineo — the biophysicist who invented this treatment.4 Training with the person whose research created the device.
The program is medically supervised by Lisa D. Persyn, M.D., board certified in Physical Medicine and Rehabilitation — the specialty built around restoring function to people living with pain, nerve injury and limb loss. The device is restricted to physicians, or to trained personnel working under a physician's supervision,1 and your care is looked at by a physiatrist as well as by the doctor running your sessions.
What that looks like in the room: placement worked out fresh at every visit; the level brought up in steps, with you saying where it stops; the setup changed on the spot when the pain isn't answering; and someone with you for the whole session.

Questions patients actually ask
Before you call
How can scrambler therapy treat a limb that isn't there?
It treats the signal, not the limb. Phantom pain comes from nerves and pathways you still have. Scrambler therapy sends a non-pain message up those same nerves, session after session, so the circuit gets a different message to hold on to.
Where do the electrodes go if the painful part is missing?
On healthy skin with normal feeling, on the body you have, along the nerve pathways that served the area that hurts — never on broken, irritated or numb skin. The exact placement is worked out by hand at your first session, with you telling us what you feel, and it's adjusted until the pain answers.
Is this for phantom sensation, or pain in my residual limb?
This page is about phantom limb pain — pain in the part that's gone. Phantom sensation that doesn't hurt is normal and doesn't need treating. Pain in the residual limb itself — skin, socket fit, bone, a neuroma — should be checked first by your prosthetist and surgeon. If they've looked and what's left is nerve pain, bring it to the consultation.
Does it hurt?
No. A properly run session feels like a comfortable tingle. If anything increases your pain, we stop and change the placement. A scrambler treatment that hurts is being done wrong.
How many sessions — and how soon will I know?
A full course is ten, on consecutive weekdays over two weeks. Many people feel the pain fall during the very first session; what matters is whether relief starts holding longer between visits, and that's usually clear within the first several days. That's what the $99 first session is for. Some people come back later for a short round of boosters.
Can I keep taking my medications?
Keep taking them for now, and don't stop anything on your own. Gabapentin, Lyrica (pregabalin) and Cymbalta (duloxetine) can all interfere with the signal scrambler therapy sends, so we'll work with the doctor who prescribed them to wean you off safely. That has to be done gradually: gabapentin and Lyrica are anticonvulsants, and stopping them all at once can cause seizures. Cymbalta can cause withdrawal symptoms if it's stopped suddenly. Bring your full medication list to the consultation.
Is it covered by insurance? I'm a veteran — can I come here?
Scrambler therapy isn't a covered insurance benefit, so the course is an out-of-pocket investment, and you'll have the number in writing before you commit. Yes, you can come here directly — no referral needed. Texas Spine Clinic is a private practice. If you have a benefit you think might apply, bring the details to the consultation.
I've had other surgery, or I have hardware. Does that rule me out?
Orthopedic hardware — plates, screws, pins, rods, joint replacements — doesn't rule out scrambler therapy. An implanted electronic device does: a pacemaker, a defibrillator, or an implanted spinal cord or peripheral nerve stimulator, including one in trial. Bring your surgical history to the consultation and we'll go through it with you.
What if it doesn't work for me?
Then we tell you, and we stop. You'll have invested $19 and $99 to get a real answer instead of more years of wondering. If it does work and you continue, that $99 comes off the course.
Footnotes
- Smith TJ, Wang EJ, Loprinzi CL. Cutaneous Electroanalgesia for Relief of Chronic and Neuropathic Pain. New England Journal of Medicine 2023;389:158–64. Review by physicians at Johns Hopkins and the Mayo Clinic — ↩
- Same review — mechanism and application: electrode placement on unaffected skin along the affected dermatomes; the continuously varied waveform sequences; the operator's step-by-step level-setting dialogue; session length; relief typically lengthening over a course; reported durability and retreatment; and the statement that scrambler therapy is distinct from TENS. ↩
- ST-5A device instruction manual (Delta International Services & Logistics, rev. 2020) — indications, warnings, contraindications, precautions and treatment protocol, including session length, the ten-treatment course structure, and the exclusions listed above. ↩
- Dr. Barton completed advanced scrambler therapy training in Rome, Italy, with Dr. Giuseppe Marineo, who developed scrambler therapy at the University of Rome Tor Vergata. ↩
- Ramachandran VS, Rogers-Ramachandran D. Synaesthesia in phantom limbs induced with mirrors. Proceedings of the Royal Society of London B 1996;263:377–86 — the first description of mirror therapy, developed for phantom limbs. ↩
Primary sources on file at the clinic.
The ask
Find out whether the signal can change.
Call (210) 741-9166. The consultation is $19 — and it isn't a sales pitch.
- The $19 consultation. About an hour, Monday through Thursday. We take your history, sort out which pain is which, examine you, and check you against the list of reasons someone can't have this treatment. If you're not a candidate, you'll hear it at that visit, along with where we'd point you instead.
- A $99 first session — credited toward the course. A full session, done properly, so you can find out what your nerves do with this before anyone talks to you about a program. If you continue, the $99 comes off the course.
- You decide, with the number in front of you. If you responded, we'll walk you through the full course, in writing. If you didn't, we'll say so — and nobody will ask you to try a few more just in case.
Texas Spine Clinic · 3212 Napier Park, San Antonio, TX 78231
Monday–Thursday, 8 a.m.–5 p.m. · Friday: scrambler therapy sessions only, by
appointment.
Book your $19 consultation
No referral needed. Same-day appointments available.
Calendar not showing? Open it in a new tab.
Rather book by phone? Call (210) 741-9166.
P.S. If you've lived with a foot or a hand that hurts and isn't there — for a few months, or for twenty years — you've heard every version of "learn to live with it." Here's a different one: a $19 consultation and a $99 session, and an early answer about whether your nerves respond. Two weeks from now, you could know. Call (210) 741-9166.