← Blog
Spine & Discs
Bulging disc or herniated disc? What the difference means for you.
Two words that get used interchangeably and shouldn’t be. What each one looks like on imaging, the symptoms that tend to follow, and how the difference shapes your care.
Somebody said “bulging disc” on the phone. The report says “broad-based protrusion.” Your brother-in-law says a bulge is just a small herniation. Everything you read online uses the two words as if they were one.
They aren’t. A bulge is not a small herniation. It is a different finding, and the difference is the difference between a tire running low and a tire with a puncture. If the words got mixed up when someone talked to you, that wasn’t you failing to keep up. They get mixed up constantly, including by people who should know better.
Start with the disc
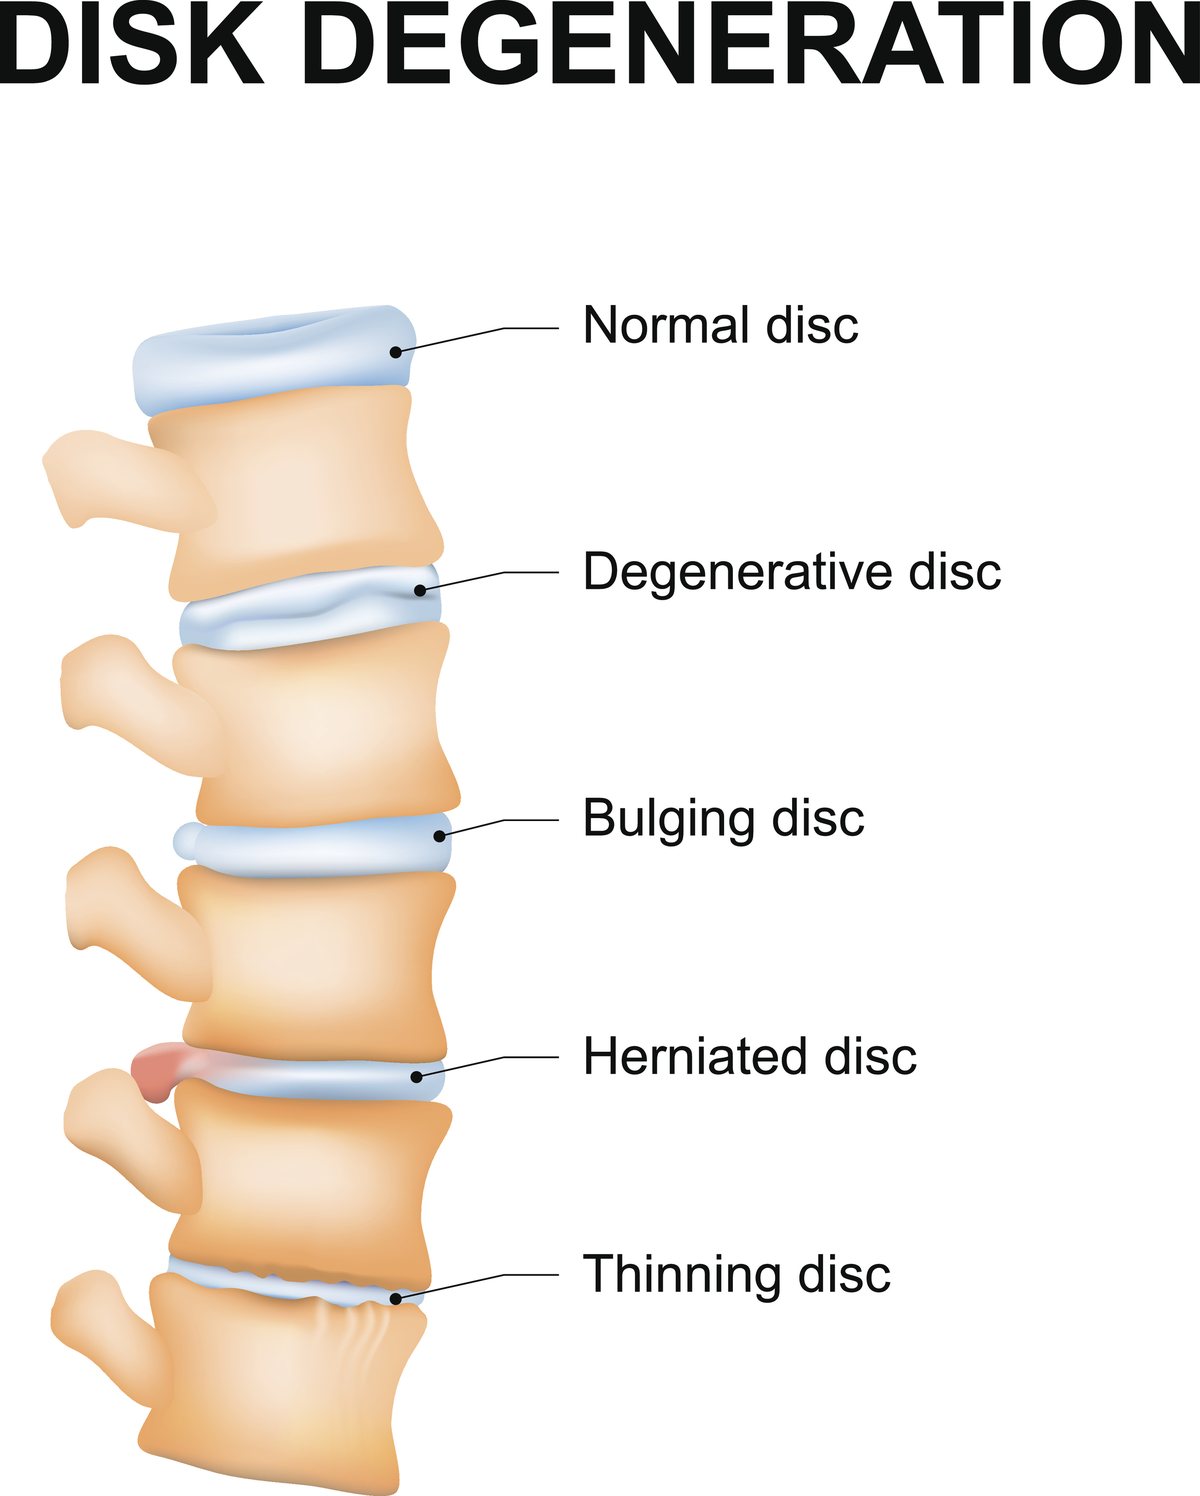
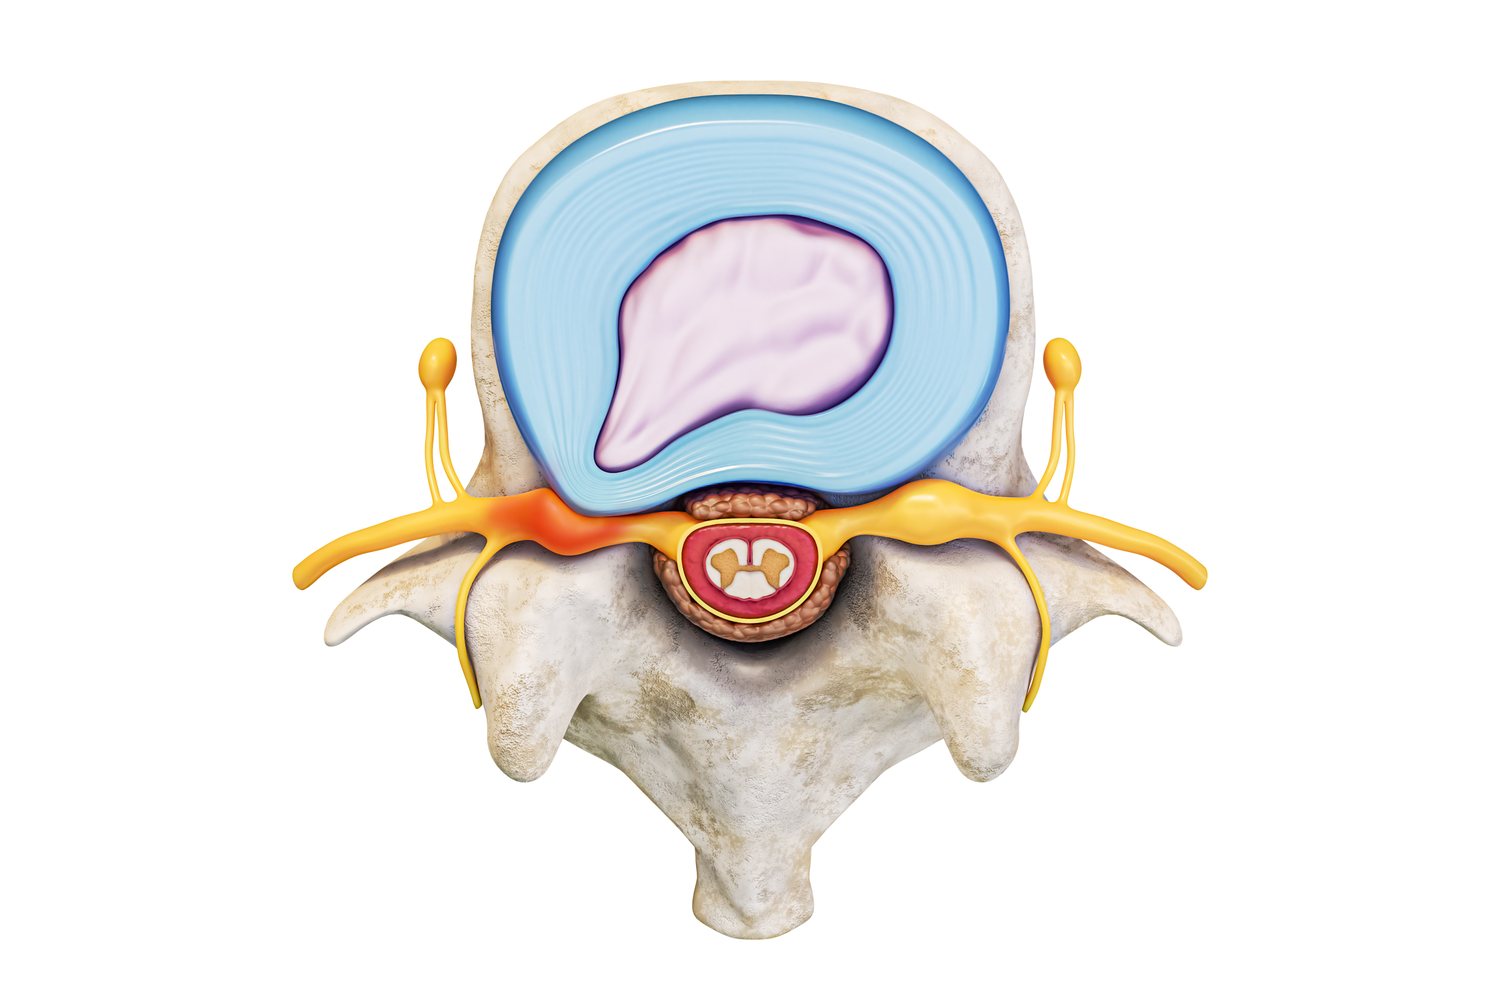
Between each pair of bones in your spine sits a disc, a shock absorber. Picture a jelly donut with a very tough shell. The shell is a ring of hard fibers called the annulus. The center is a soft, water-rich gel called the nucleus. Now the four words your report might use. They are a ladder, not four different diseases; they describe increasing amounts of the same thing.
- Bulge. The whole disc is squeezed enough that it spreads past its normal edge, like a tire with low air. The shell is intact. It’s just being pushed wide under the weight.
- Protrusion. Inner material has pushed through part of the shell and is sticking out, but the base is still wider than the part that’s poking out. Think of pressing your thumb into the inside of a balloon: a broad, contained lump.
- Extrusion. The material has squeezed all the way through the shell, and the part outside is now wider than the neck it came through. Toothpaste pushed through a small hole and mushrooming on the other side.
- Sequestration (a “free fragment”). A piece has broken off completely and is sitting loose in the canal.
“Herniation” is the umbrella word for the bottom three. A protrusion is a herniation. An extrusion is a herniation. A sequestration is a herniation. A bulge is not.
Two more things patients always want to know
A bulge is wide, and a herniation is focal. A bulge usually involves a broad stretch of the disc’s rim rather than one spot, which is why your report probably says “broad-based.” A herniation is one place. That is part of why a bulge is less likely to be jammed into a single nerve.
“Bulge” describes a shape, not a diagnosis. It tells you what the disc looks like. It does not tell you whether that disc is what hurts. Bulges show up on the scans of plenty of people with no back pain at all, which is why a bulge on a report is a reason for an exam, not a reason for alarm.
A bulge is a squashed disc with an intact shell. A herniation is a disc whose shell has been breached. Protrusion, extrusion and sequestration describe how far through the material got.
The symptoms that tend to follow
Because a bulge is broad and contained, when it does cause trouble it tends to cause it locally: a deep, achy low back or neck, stiffness that is worse after sitting, pain that stays near the spine. Because a herniation is focal and often pointed at a nerve, it tends to cause the symptoms that travel: sciatica down the leg, pain into the arm, tingling in the toes or fingers, and in the more serious cases weakness, a foot that won’t lift or a grip that isn’t there.
That is a tendency, not a law. A big broad bulge in an already narrow canal can pinch a nerve. A small herniation pointed at empty space can hurt very little. The pattern of your symptoms, checked against the level and direction on the MRI, is what tells us which finding is the one that hurts. Here is how we read the rest of the report.
Does a bulge turn into a herniation?
Some do. Most don’t. And nobody can look at your report and tell you which one you’re holding, so be careful with anyone who says they can.
What we can tell you is the mechanism. The shell of a disc isn’t one solid wall. It is built in layers, like a radial tire, sheets of tough fibers running in alternating directions. That design is extremely good at handling pressure, and it is why a bulging disc can spread outward for years without anything giving way. What wears it down is repetition, not force. Under years of load, and especially in a disc that has already lost water and flattened, small tears can develop between those layers, starting from the inside. If enough of them line up into a path through the shell, inner material can start to follow that path outward. When that finally happens the moment itself is usually unremarkable. “All I did was bend over to pick up a sock.”
What is worth watching isn’t your imaging. It’s whether symptoms are travelling further down your leg or retreating back toward your spine.
Why does sitting make it so much worse? Not because a chair presses harder than standing; the measurements don’t support that. It’s that a chair holds the load steady and never lets up, and a disc under sustained pressure slowly gives. Bending forward and lifting is what loads a disc hardest. Long sitting aggravates an injured one for a different reason: the pressure never comes off.
How the difference shapes your care
This is where the two words stop being vocabulary and start being a plan.
- A bulge that isn’t touching a nerve is usually a joint, muscle and movement problem, and it responds to care aimed there: chiropractic adjustment to free the stiff segments, and strengthening so the disc carries less of the load.
- A bulge or a herniation that is pressing on a nerve is a decompression conversation. Spinal decompression aims at the disc itself, lowering the pressure inside it so the material can draw back off the nerve. It is used for bulging discs, herniated discs and degenerative discs alike, when the disc is the thing causing the pain.
- A free fragment is a different conversation, and depending on your symptoms and its size it can be a reason we won’t treat. One more reason we look at your actual images before anyone talks about a plan.
Too young for this. Also too young for a fusion.
Early-stage disc problems show up in people in their twenties more often than anyone expects, and the usual advice is to wait. This patient didn’t.
 Watch
 Watch
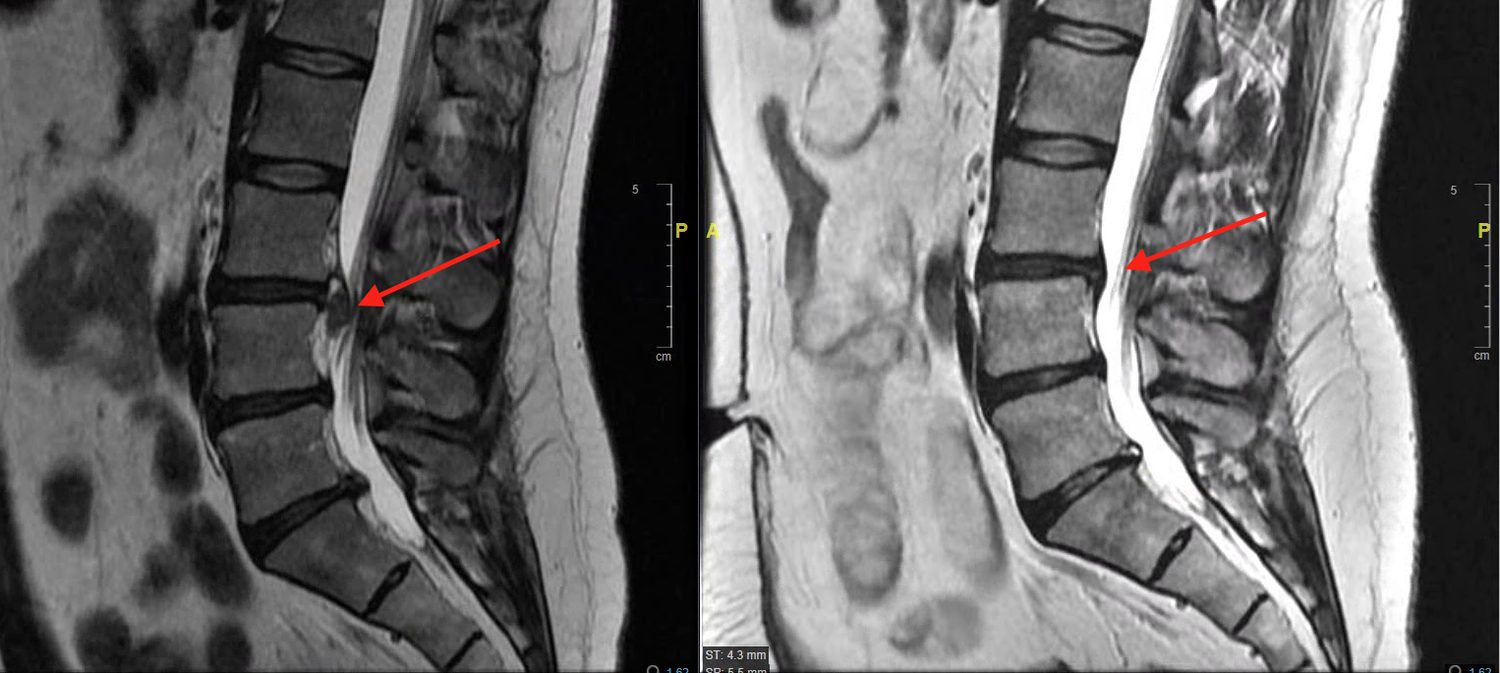
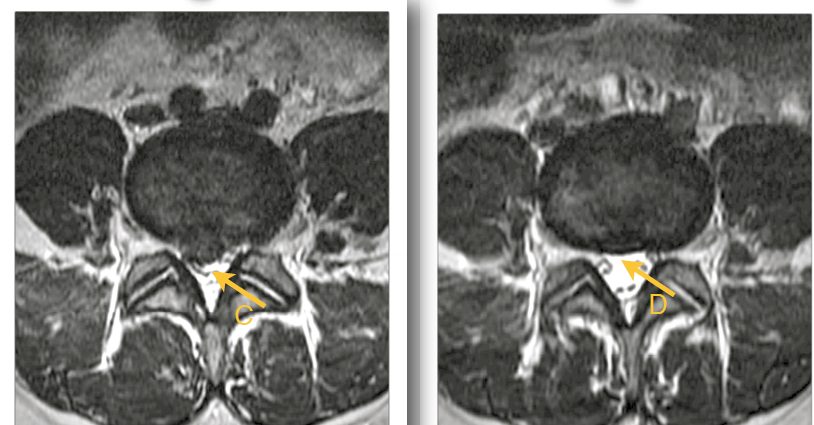
The doctor's own disc, episode 2Reading his own MRIHow the words on the report look on the actual pictures.
 Watch
The four tissues behind back painWhy a disc problem is never only a disc problem.
Find out which one you have, and whether it’s the one that hurts
Bring the report. The $49 DRX9000 consultation is an exam first, then your MRI on the screen with you at the second visit, finding by finding, so you leave knowing which word applies to you, what it is touching, and what we plan to do about it.
Book the $49 DRX9000 consultation
This article is educational and is not a substitute for an examination and diagnosis. Individual results vary and no outcome is guaranteed.