← Blog
Spine & Discs
Your MRI says “herniated disc.” Here’s what the report actually means.
Protrusion, extrusion, foraminal narrowing, “clinical correlation recommended.” A plain-English walk through the words on your report, which ones matter, and how we connect what’s on the screen to what you feel every day.
These days the report usually reaches you before the doctor does. It lands in the patient portal on a Tuesday night, and by Wednesday morning you have read it four times and looked up half of it. Broad-based protrusion. Foraminal narrowing. Effacing the thecal sac. Every line sounds like a verdict.
Here is the first thing to know: a radiology report is written by one doctor for another, in a shorthand built to be precise, not comforting. The radiologist is describing everything the scan shows, in order, whether or not it has anything to do with why your leg hurts. Almost every scary word on the page has a boring meaning. This article translates the ones that matter.
Nobody showed you the pictures. There’s a reason.
Patients tell us all the time that they had an MRI, got a two-line summary over the phone, and never saw a single image. Nobody did anything wrong. A referring doctor gets the written report, not a monitor with your films on it, and a fifteen-minute appointment doesn’t leave room to walk a patient through twenty slices of their own spine.
But the pictures are the point. The report tells you what is there. The pictures, next to a proper exam, tell you what is pressing on what, and whether that explains the pain you actually have. So before the vocabulary, one rule that runs through everything below:
A finding on an MRI only counts when the exam agrees with it. The scan tells us where to look. Your body tells us whether we found it.
Start with the disc itself
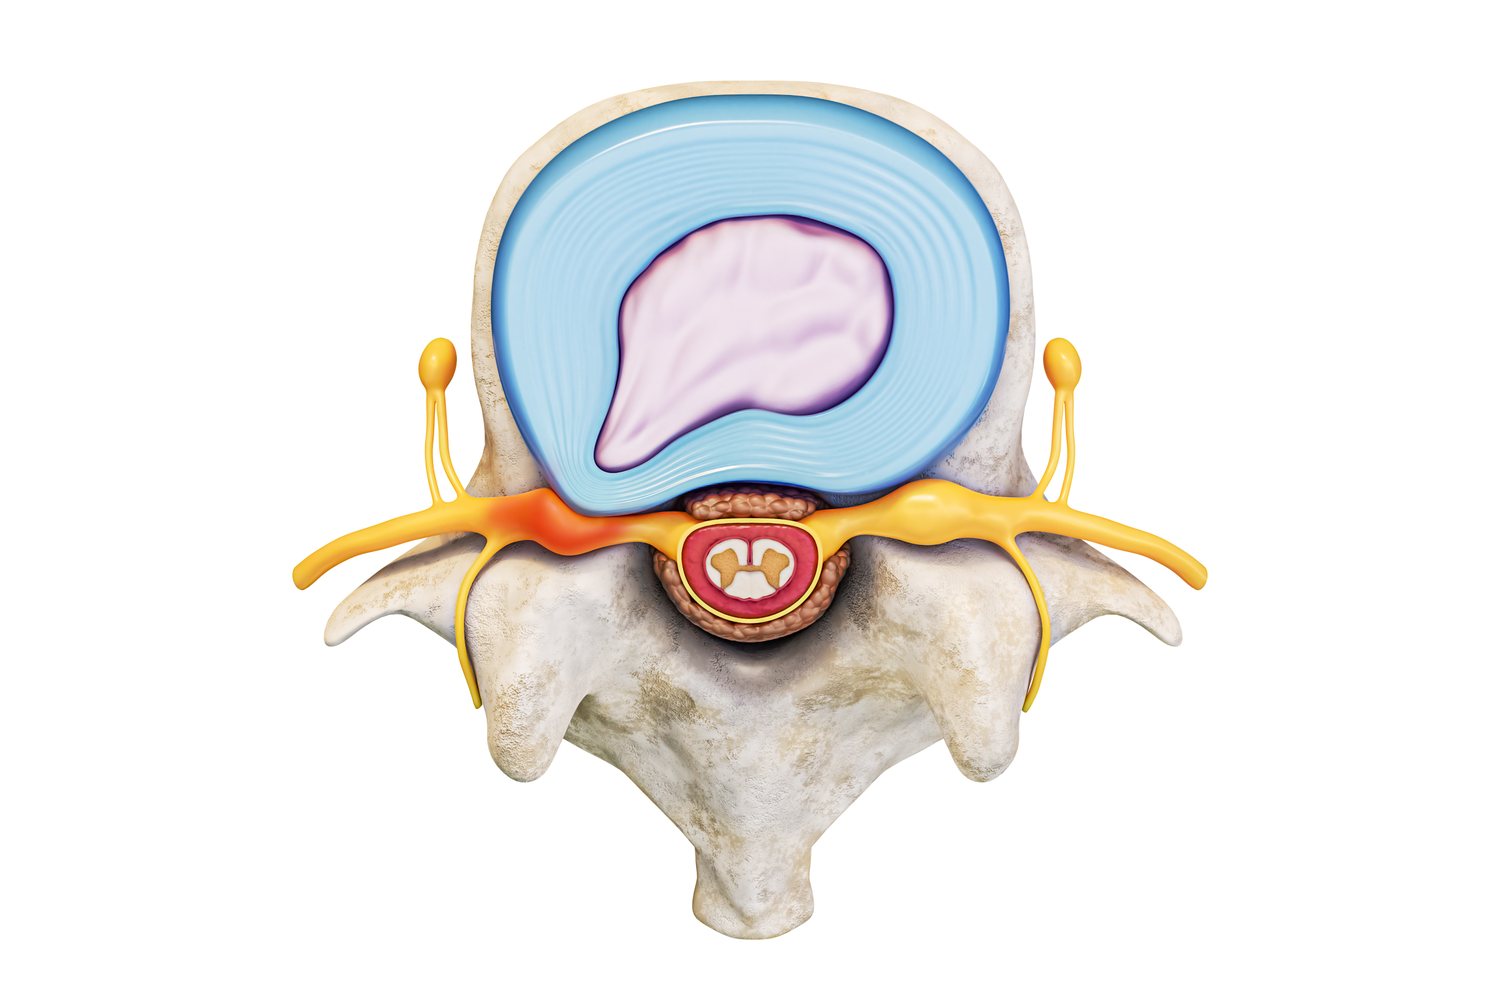
Between each pair of bones in your spine sits a disc, a shock absorber. Picture a jelly donut with a very tough shell. The shell is a ring of hard fibers called the annulus. The center is a soft, water-rich gel called the nucleus. A healthy disc is roughly 90% fluid, and that water is what lets it carry load all day.
Nearly everything a lumbar report says about a disc is one of three things:
- How much water is left. “Desiccation” means the disc has dried out some. “Loss of disc height” means it has flattened as a result. Both describe mileage on the disc, not damage to a nerve.
- Whether the shell gave way. An “annular fissure” is a crack in the shell. A “high-intensity zone” is that crack lit up on the scan. The four words below describe how far the inside got through it.
- What it’s touching now. “Contacting,” “impinging,” “effacing the thecal sac,” “foraminal narrowing.” These are the words about the nerve, and they are the ones that matter most.
Four words, one ladder
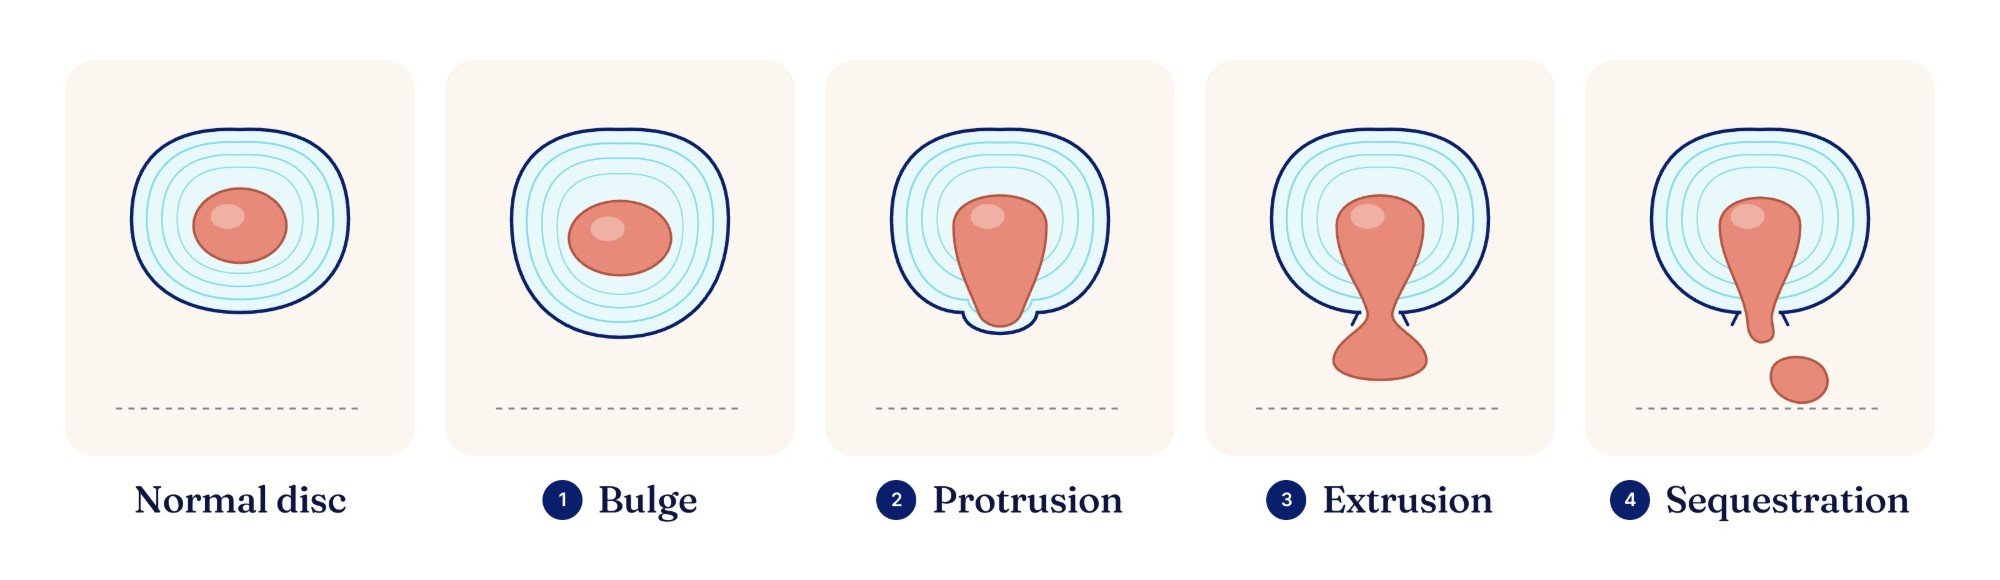
Bulge, protrusion, extrusion, sequestration. They get used as if they were interchangeable, and they aren’t. They describe increasing amounts of the same thing.
- Bulge. The whole disc is squeezed enough that it spreads past its normal edge, like a tire with low air. The shell is intact. A bulge is not a herniation, and most bulges never become one.
- Protrusion. Inner material has pushed through part of the shell and is sticking out, but the base is still wider than the part that’s poking out. A broad, contained lump.
- Extrusion. The material has squeezed all the way through the shell, and the part outside is now wider than the neck it came through. Toothpaste pushed through a small hole.
- Sequestration (a “free fragment”). A piece has broken off completely and is sitting loose in the canal.
“Herniation” is the umbrella word for the bottom three. A bulge is not one. If you’ve been reading about herniated discs and quietly assuming it applies to you, it may not. We wrote a whole article on that one difference, because it changes the plan.
Bigger on paper isn’t more painful. “Extrusion” sounds much worse than “protrusion,” and it is bigger. It is not automatically more painful. And the dramatic-looking ones are often the ones most likely to shrink over time, which is its own conversation.
The millimetres matter less than where it’s pointing
Patients fix on the number. “Seven millimetres” sounds enormous. What decides whether a herniation hurts is not its size but its direction, because the nerves leave the spine through specific openings, and a disc that pushes toward one of them is a very different problem from a disc that pushes toward empty space.
- Central. Straight back, toward the middle of the canal. Often back pain more than leg pain, because there is room there.
- Paracentral. Back and slightly to one side, where the nerve root is just setting off on its way down. This is the classic sciatica position.
- Foraminal. Out toward the doorway the nerve exits through. Less room, and often a sharper, more specific leg or arm pain.
The level should match your symptoms
Each disc sits beside a particular nerve, and each nerve runs to a particular part of the leg or arm. That’s the map we use to check the report against you.
- L3-L4. Front of the thigh, across the knee. Weakness shows as a knee that gives out.
- L4-L5. Outside of the calf, across the top of the foot, into the big toe. Weakness shows as trouble lifting the front of your foot, the “foot drop.”
- L5-S1. Back of the thigh and calf, the heel, the outer foot and little toes. Weakness shows as trouble pushing off or standing on your toes.
- In the neck, C6 runs down the arm into the thumb and index finger, C7 into the middle finger.
If the report names L5-S1 and your pain runs down the front of your thigh, something doesn’t add up, and that mismatch is worth more than any single line on the page. It is exactly the thing an exam is for.
“Degenerative changes” describes mileage, not a prophecy
This is the phrase that frightens people most, and it is the one that usually matters least. Discs dry out and flatten a little with age. Facet joints roughen. Ligaments thicken. Radiologists report all of it, because that is their job, and much of it shows up on the scans of adults who have no back pain at all. It is not a countdown. It is a description of a spine that has been used.
The line at the bottom, “clinical correlation recommended,” is the radiologist saying the same thing we are: somebody needs to examine this patient and decide which of these findings is the one that hurts.

What a real MRI review looks like
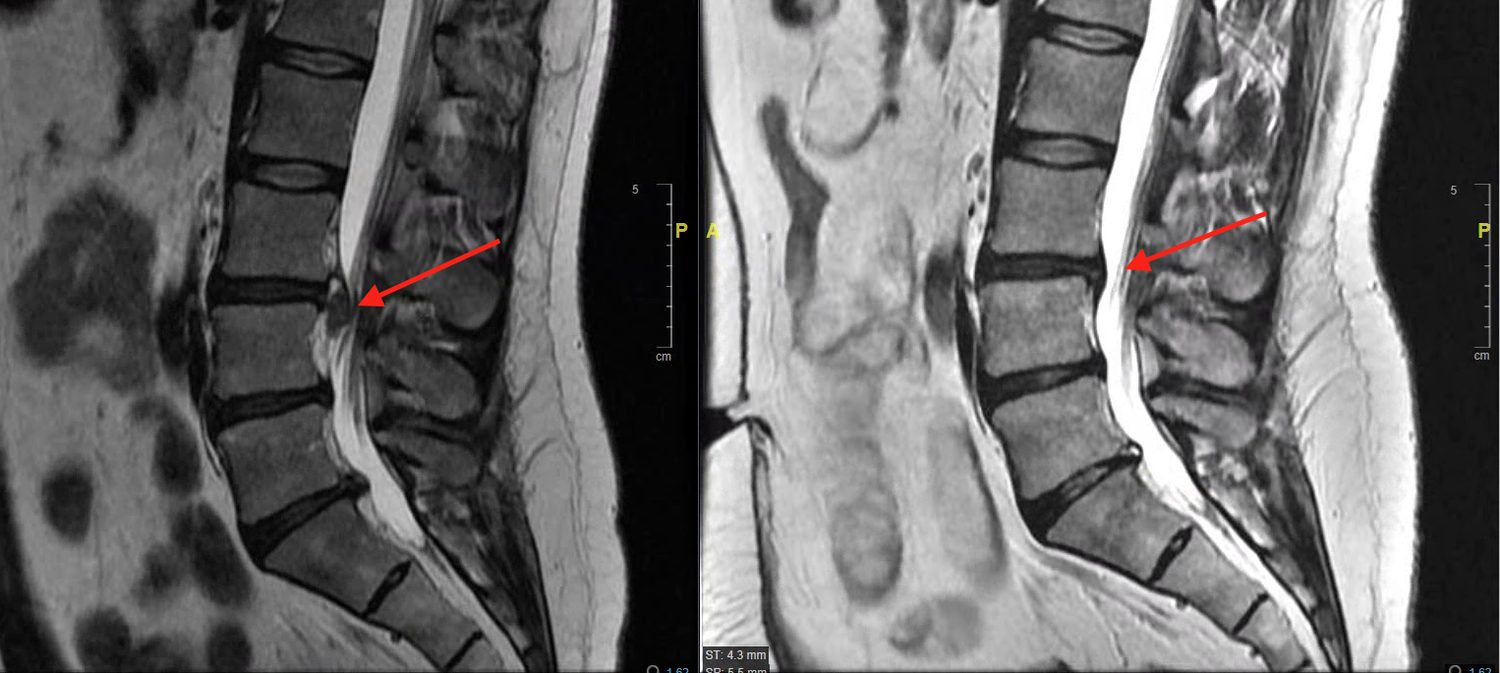
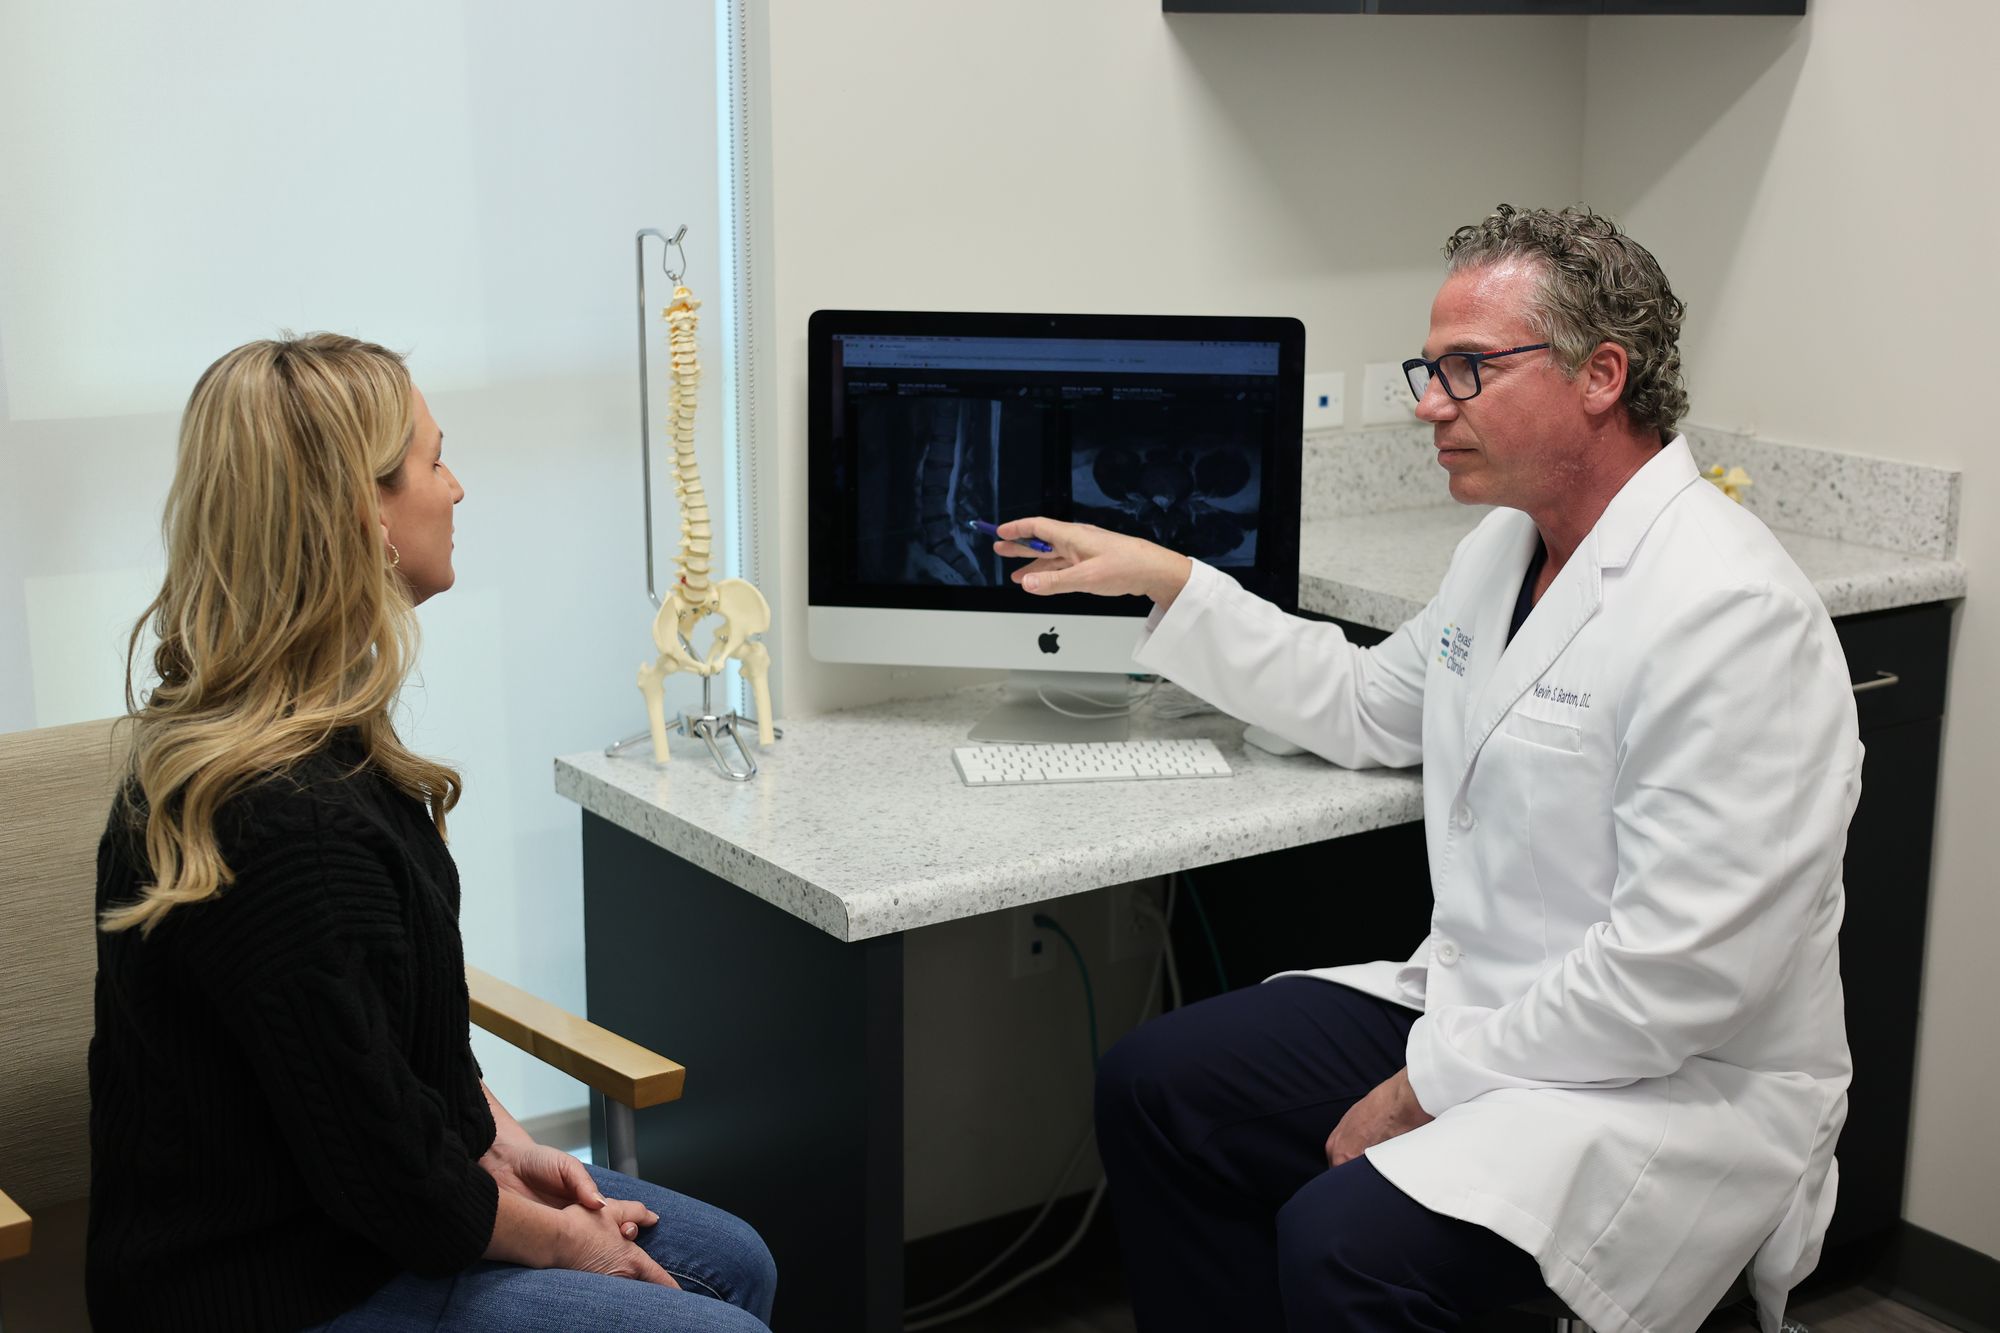
Dr. Barton put his own lumbar MRI on the screen and read it on camera, the same way he reads yours: slice by slice, pointing at what is pressing on what. If you want to see what a finding looks like next to a nerve, rather than read about it, start here.
 Watch
Episode 1The MRI, uneditedAn L4-L5 ruptured disc. His own films, on the screen, nothing left out.
 Watch
Episode 2Reading his own MRIHow he reads a lumbar MRI, slice by slice. The same review you get at your second visit.
At Texas Spine Clinic, that review is part of the $49 DRX9000 consultation: your exam at the first visit, and at the second, your MRI on the screen with you, a straight answer about what is causing your pain, and a plan in writing. Bring the report nobody explained.
Want the full glossary? Our MRI report, in plain English page translates every term on a sample report, including the ones we skipped here: Modic changes, facet arthropathy, ligamentum flavum, spondylolisthesis and more.
Book the $49 DRX9000 consultation
This article is educational and is not a substitute for an examination and diagnosis. Individual results vary and no outcome is guaranteed.